University of Maryland School of Medicine logo
Emergency Medicine
All Departments
UMSOM Assistant

UMEM Educational Pearls

  • Home
  • Departments
  • Emergency Medicine
  • CME
  • UMEM Educational Pearls
  • CME
  • Courses and Conferences
  • Free Open Access Medical Education
  • UMEM Educational Pearls
Previous  |  1 |  2 |  3 |  4 |  5 |  6 |  7 |  8 |  9 |  10 |  11 |  12 |  ... |  239 |  Next

Title: Can US be effectively used in the prehospital setting?

Category: EMS

Keywords: prehospital, EMS, ultrasound (PubMed Search)

Posted: 4/12/2026 by Robert Flint, MD (Updated: 4/12/2026)

This German retrospective study compared the prehospital use of ultrasound by trained paramedics and compared their findings to in-hospital diagnosis and image results. The authors found: 

“Diagnostic accuracy, defined as the concordance between prehospital POCUS-based working diagnoses and final in-hospital diagnoses, was particularly strong for lung ultrasound (pneumothorax, pulmonary edema, pneumonia and pleural effusion; sensitivity 91.7%, specificity 100%) and eFAST (sensitivity 100%, specificity 96.5%), while for the abdominal ultrasound examinations, the specificity was 70% and sensitivity was 71.43%.”

This study sets the stage for future prospective work looking at prehospital US use by paramedics.

Show References

Boehm, A., Bexten, T., Stanley, M. et al. Feasibility and diagnostic accuracy of paramedic-performed prehospital point-of-care ultrasound: a retrospective observational study. Scand J Trauma Resusc Emerg Med (2026). https://doi.org/10.1186/s13049-026-01595-4


Title: Does my child have a concussion?

Category: Orthopedics

Posted: 4/11/2026 by Brian Corwell, MD

What elements of the history are most helpful for diagnosing a concussion?

An estimated 1.1 million to 1.9 million pediatric concussions occur annually in the US.

Show Additional Information

Does my child have a concussion?

OBJECTIVE: To determine the accuracy of clinical history for identifying concussion in children and adolescents.

While most children recover within 4 weeks, approximately 30% experience persistent symptoms beyond 28 days. 

Early evaluation and timely management are associated with improved recovery—athletes who immediately reported their injury experienced almost five and half fewer days of symptoms compared to those who delayed reporting. 

Key Diagnostic Findings

The review identified the most diagnostically useful symptoms (by likelihood ratio):

Finding Likelihood Ratio (LR+) Specificity
Mental fog 11.8–12.0 0.96
Noise sensitivity 6.9 0.94
Nausea 6.7 0.93
Light sensitivity 6.4 0.93
Headache 3.1 0.74

The ABSENCE of headache was the only finding that substantially reduced the likelihood of concussion (LR, 0.20; sensitivity, 0.86)

Show References

Shah SN, Chizuk HM, Fong H, Hannon M, Mannix RC. Does This Child Have a Concussion? The Rational Clinical Examination Systematic Review. JAMA. 

Published online April 06, 2026.


Title: Best Practices for the <12 month old's airway

Category: Pediatrics

Keywords: pediatrics, airway, intubation, infant, neonate (PubMed Search)

Posted: 4/10/2026 by Kat Stephanos, MD (Updated: 9/17/2026)

BOTTOM LINE:

  • Use of VL and cuffed ETTs are appropriate for all ages
  • Hyperangulated blades, LMAs and scopes should be available for rescue
  • Apneic oxygenation is useful in neonates. 

A 2024 meta analysis from the European Society of Anaesthesiology and Intensive Care and British Journal of Anaesthesia worked to develop joint guidelines for best practices for intubation of neonates and infants. 

While this guide is focused primarily on anesthesia and operative care, several of the recommendations have practical application to the EM and ICU as well. 

They focused on general guidance including ensuring appropriate anesthesia and analgesia during intubation. But also discussed that videolaryngoscopy with standard blades is the most appropriate first line for all intubations in this age group. It allows for appropriate visualization either directly or by video and for learners allows instructors to observe as well. 

When there are difficulties with intubation, hyperangulated blades have very high success rates, but LMA and video assisted intubation with a fiberoptic scope are also appropriate next steps for securing an airway. 

When intubating, uncuffed endotracheal tubes are acceptable in all infants though cuffed are also safe in infants over 3kg in weight.

Finally, while apneic oxygenation is regularly used in adults, it is also recommended in the neonatal period to avoid hypoxia.

Show References

Disma N, Asai T, Cools E, Cronin A, Engelhardt T, Fiadjoe J, Fuchs A, Garcia-Marcinkiewicz A, Habre W, Heath C, Johansen M, Kaufmann J, Kleine-Brueggeney M, Kovatsis PG, Kranke P, Lusardi AC, Matava C, Peyton J, Riva T, Romero CS, von Ungern-Sternberg B, Veyckemans F, Afshari A; and airway guidelines groups of the European Society of Anaesthesiology and Intensive Care (ESAIC) and the British Journal of Anaesthesia (BJA). Airway management in neonates and infants: European Society of Anaesthesiology and Intensive Care and British Journal of Anaesthesia joint guidelines. Eur J Anaesthesiol. 2024 Jan 1;41(1):3-23.


Title: Tenecteplase Strikes Out for CRAO

Category: Pharmacology & Therapeutics

Keywords: central retinal artery occlusion, tenecteplase, thrombolytic (PubMed Search)

Posted: 4/9/2026 by Alicia Pycraft (Updated: 4/9/2026)

TenCRAOS was a phase 3 randomized, multi-center, double blind, double dummy, placebo-controlled trial in 78 patients that showed no significant difference in visual outcomes at 30 days for IV tenecteplase 0.25 mg/kg compared to aspirin 300 mg alone within 4.5 hours of central retinal artery occlusion (CRAO) symptom onset. Tenecteplase was associated with more serious adverse events, one of which was a fatal intracerebral hemorrhage.  

Bottom line: Although tenecteplase has theoretical advantages in CRAO, the results of this trial do not support routine use.

Show Additional Information

Study design:

  • Phase 3 randomized, multi-center, double blind, double dummy, placebo-controlled trial
  • Included patients with CRAO diagnosed with best corrected visual acuity (BCVA) of 1.0 log-MAR or greater in the affected eye and were able to receive treatment within 4.5 hours
  • Interventions: Tenecteplase 0.25 mg/kg (max of 25 mg) + oral placebo vs. oral aspirin 300 mg + IV placebo (randomized 1:1)
  • Primary endpoint: BCVA of 0.7 log-MAR or lower in the affected eye at 30 days after treatment (Considered a clinically meaningful improvement in visual acuity on the Early Treatment Diabetic Retinopathy Study Chart)

Results:

  • 78 patients included in final analysis (40 in tenecteplase group and 38 in aspirin group)
  • No significant difference in the number of patients with BCVA of 0.7 log-MAR or lower for tenecteplase compared to aspirin (20% vs 24%, risk difference -0.04 (-0.22 to 0.15). Result was consistent across all visual efficacy endpoints and among a subgroup of patients treated within 3 hours of symptom onset.
  • Adverse events occurred in 48% of patients in the tenecteplase group and 34% in the aspirin group.
    • More serious adverse events in the tenecteplase group (10 events among 8 patients vs. 4 events among 4 patients in the aspirin group)
    • One serious adverse event attributed to tenecteplase was fatal. Event involved ongoing cerebral ischemia that was not apparent on head CT or clinically. Multiple intracerebral hemorrhages caused by reperfusion of damaged brain tissue developed after tenecteplase administration.

Show References

Ryan SJ, Jørstad ØK, Skjelland M, Pesonen M, Simonsen CZ, Bek T et al.  A randomized trial of tenecteplase in central retinal artery occlusion. N Engl J Med. 2026. 394(5): 442-450.


Title: Gender affects trauma triage and care

Category: Trauma

Keywords: trauma, treatment disparity, gender (PubMed Search)

Posted: 4/8/2026 by Robert Flint, MD (Updated: 4/8/2026)

This systematic literature review looking at gender differences in trauma care reveals:

  1. Women were older with more low-energy trauma than men. 
  2. Women were more likely to suffer from pelvic and spinal cord injuries. 
  3. Women were more likely to be under-triaged and under-treated.
  4. Sex/gender-based differences in mortality were inconsistent across studies. 
  5. Adjusted mortality appeared similar between women and men

Show References

Ghika-Nanchen, A., Marzorati, L., Merra, A. et al. Sex and gender bias in major trauma care: a scoping review. Scand J Trauma Resusc Emerg Med (2026). https://doi.org/10.1186/s13049-026-01596-3


Title: High-Flow or Standard Oxygen for Acute Hypoxemic Respiratory Failure?

Category: Critical Care

Posted: 4/7/2026 by Mike Winters, MBA, MD

In a large, randomized trial conducted in 42 ICUs in France, high-flow oxygen did not reduce 28-day all-cause mortality in adult patients with acute hypoxemic respiratory failure when compared to standard oxygen support.

Show Additional Information

The SOHO Trial

  • An investigator-initiated, open-label RCT
  • Conducted in 42 ICUs in France
  • Included adult patients who were admitted to the ICU with acute hypoxemic respiratory failure
  • Excluded patients with a COPD exacerbation, chronic lung disease, acute cardiogenic pulmonary edema, hemodynamically unstable, or those who needed emergent intubation.
  • Patients were randomized to either a High-Flow oxygen group or a Standard oxygen group.
  • The primary outcome was 28-day all-cause mortality.
  • Secondary outcomes included intubation by day 28, ventilator free days, ICU mortality, in-hospital mortality, 90-day mortality, and ICU/hospital LOS.
  • A total of 1,110 patients were included in the intention-to-treat analysis.  The High-Flow group had 556 patients and the Standard group had 554 patients.
  • The primary outcome occurred in 14.6% of patients in the High-Flow group and in 14.6% of patients in the Standard group.
  • With respect to secondary outcomes, the incidence of intubation at day 28 was lower in the High-Flow group.  In addition, the high-flow appeared to reduce dyspnea scores, and improve respiratory rates and CO2 values.
  • Limitations of the SOHO trial included a lower than expected mortality (underpowered) and a high percentage of patients with viral pneumonia.


Title: Geriatric learning objectives for prehospital providers

Category: Geriatrics

Keywords: prehospital, geriatric, education (PubMed Search)

Posted: 4/5/2026 by Robert Flint, MD (Updated: 4/5/2026)

A  modified 2 round Delphi study was used to create 57 learning objectives in geriatric care for European prehospital providers.  Based on in-hospital learning objectives and literature, these experts came up with what appears to be a very reasonable and helpful list of education objectives for pre-hospital providers that could easily apply to emergency medicine learners as a whole. Here is their table:

https://link.springer.com/article/10.1186/s13049-026-01550-3/tables/3

Show References

Krohn, JN., Barrett, J., Heeren, P. et al. A European paramedic curriculum for geriatric emergency medicine developed via a modified Delphi technique. Scand J Trauma Resusc Emerg Med 34, 14 (2026). https://doi.org/10.1186/s13049-026-01550-3


Title: Older patient splenic injury outcomes

Category: Trauma

Keywords: splenic injury, geriatrics, mortality (PubMed Search)

Posted: 4/4/2026 by Robert Flint, MD (Updated: 9/17/2026)

In this retrospective cohort study looking at splenic injury management and outcomes in the UK, patients over age 65 had much higher mortality and were more often managed conservatively (vs splenectomy or embolization) despite having a lower splenic injury grade and lower overall injury severity score compared to those under 65. Many factors are possible here including frailty, reluctance to intervene in older patients, and lower mechanism of injury bias away from evaluation and management.

Show References

Jenkins P, Anton B, Blair G, et al. Traumatic splenic injury in the elderly population: Does management choice affect outcome? Trauma. 2026;0(0). doi:10.1177/14604086261430458


Title: Rigid or soft-it may not matter

Category: Trauma

Keywords: Cervical immobilization, collar rigid, soft (PubMed Search)

Posted: 4/2/2026 by Robert Flint, MD (Updated: 9/17/2026)

Looking at trauma patients evaluated at a major trauma center before and after EMS switched from semi-rigid to soft cervical collars for immobilization found no difference in adverse outcomes.  Add this to the mounting evidence that our current practice of spinal immobilization may not offer any benefit.

Show References

JACEP Open 2024;5:e13239. https://doi.org/10.1002/emp2.13239


Title: Marijuana Edibles: A Dangerous Treat

Category: Toxicology

Keywords: Edibles, Marijuana, Cannabis (PubMed Search)

Posted: 4/1/2026 by Kathy Prybys, DO

Bottom Line:  Edible marijuana products have high potential for overdose, particularly in children, as they are commonly mistaken for appealing food or candy, have had exponential growth in availability and ease of access in homes, can be present in very large doses due to lack standardization and quality control, and users often have confusion regarding dosing due to its long and erratic absorption and time to peak effect which may lead to redosing.

Regulation of Cannabis-Infused Edibles - Network for Public Health Law

Show Additional Information

Edibles refers to food or drink products infused with cannabis extracts. Cannabis contains numerous biologically active substances most notably delta-9-tetrahydrocannabinol (THC) which mediate most of the psychoactive effects by CB1 receptor agonism. 

Edible products include candy (gummies, hard candies, lollipops), baked goods (cookies, brownies), infused beverages, cooking oils and butters, and lozenges. Edibles are often packaged in multiple dose containers and may contain large doses of THC (up to 500 mg).  A single unit typical dose is 5 mg with 1-5 mg considered microdoses and doses > 100 mg being considered very high dose for an adult.

Onset of peak effects are 30 mins- 2 hours (up to 8 hours) because of gastrointestinal aborption of orally consumed cannabis. This range of timing may lead to overdose as individuals ingest more edibles (redosing) assuming they are not being affected.

Children >6 year of age are at special risk for edible marijuana toxicity. Most pediatric exposures (97.7%) occur in a residential setting. Weight-based dose is a substantial predictor of severe toxicity and duration of symptoms: ranging from somnolence, lethargy, nausea, and vomiting to more severe effects of respiratory depression and failure, altered mental status, seizures, and unresponsiveness. Studies report a 70% incidence of central nervous system depression with 22.7%  admitted to the hospital. Symptoms typically presented 2- 4 hours after ingestion. Patients with severe toxicity experienced symptoms for 6 hours and greater.  A few deaths have been reported.

Unintentional marijuana ingestion should be considered in the differential diagnosis of patients < 6 years of age who present with acute onset of somnolence, altered mental status,or  lethargy.

Show References

Packaging of Cannabis Edibles, Health Warning Recall, and Perceptions Among Young Adults. Cooper M, Shi Y. JAMA Netw Open. 2025;8(4):e253117. doi:10.1001/jamanetworkopen.2025.3117

Tweet MS, Nemanich A, Wahl M. Pediatric Edible Cannabis Exposures and Acute Toxicity: 2017-2021. Pediatrics. 2023 Feb 1;151(2):e2022057761. doi: 10.1542/peds.2022-057761. PMID: 36594224.

Packaging Regulations Needed to Mitigate THC Ingestions in Children. Zwiebel H, Goldman RD, Greenky D. JAMA Health Forum. 2025;6(7):e252628. doi:10.1001/jamahealthforum.2025.2628

The evolving landscape of cannabis edibles,  Blake A,  Nahtigal I.  Current Opinion in Food Science, Volume 28, 2019, Pages 25-31, ISSN 2214-7993, https://doi.org/10.1016/j.cofs.2019.03.009.


Title: New Risk Classification for PE from 2026 Guidelines

Category: Critical Care

Posted: 3/30/2026 by Jessica Downing, MD

The 2026 Acute Pulmonary Embolism Guidelines recommend a new approach to risk stratification of patients with acute PE, including measurement of at least one cardiac biomarker and serum lactate, evaluation of RV size and function with CTA or echo (preferred when feasible), and multidisciplinary PERT assessment for all patients with acute PE and elevated clinical severity scores to assist with further risk stratification.

Show Additional Information

Initial management strategies are based on these risk classifications. Inclusion of assessment of clot burden into risk stratification and management decisions is not recommended.

From a critical care perspective, we are most interested in patients in Classes C, D, and E. 

  • Class C: Normotensive but with elevated risk stratification scores (Bova, PESI, ePESI, and Hestia) with or without abnormal RV size or function on CT or echo (echo preferred when feasible), elevated biomarkers of cardiopulmoary dysfunction (trop, BNP)
  • Class D: “Pre-cardiopulmonary failure states,” including transient hypotension (for example, improving after a small IVF bolus) or normotensive shock (indicated by persistent lactate elevation >2, acute AKI,  UOP <720mL/24h, CI <2.2, or other marker of persistent poor perfusion or end-organ dysfunction)..
  • Class E: Cardiopulmonary failure (historically “high risk” or “massive” PE) with persistent or recurrent hypotension, refractory cardiogenic shock, or arrest.
  • Each of these classes can also be tagged with a respiratory modifier: hypoxia or tachypnea with RR >30 for class C, need for >6L NC for D, or respiratory failure requiring NIV or IMV for E.

Initial Management:

  • Addressing the Clot:
    • LMWH for everyone Class C and above (though maybe UFH in arrest). Start AC before consulting PERT.
    • Consider systemic thrombolysis, catheter-directed lytics, or mechanical thrombectomy for patients in Class D or E1, and systemic thrombolysis for E2. (UMMC has been involved in trials for catheter directed lytics and mechanical thrombectomy recently, with more results expected soon)
  • Hemodynamic Support: 
    • Vasopressor and/or inotropic therapy for Class D2 and above
    • Consider VA-ECMO for Category E2 (note that systemic thrombolysis is not a contraindication to VA-ECMO - some centers are more liberal with VA-ECMO, including select patients with normotensive shock or shock)
  • Transfer
    • Hemodynamically stable patients with high risk PE may be considered for transfer to centers that can provide advanced therapies, including thrombectomy or VA-ECMO
    • Unstable patients should be stabilized prior to transfer

This infographic from the new guidelines summarizes treatment recommendations. Note that institution and system-specific guidelines and PERT approaches may not yet have shifted to use these criteria.

Show References

Creager MA, Barnes GD, Giri J, Mukherjee D, Jones WS, Burnett AE, Carman T, Casanegra AI, Castellucci LA, Clark SM, Cushman M, de Wit K, Eaves JM, Fang MC, Goldberg JB, Henkin S, Johnston-Cox H, Kadavath S, Kadian-Dodov D, Keeling WB, Klein AJP, Li J, McDaniel MC, Moores LK, Piazza G, Prenger KS, Pugliese SC, Ranade M, Rosovsky RP, Russo F, Secemsky EA, Sista AK, Tefera L, Weinberg I, Westafer LM, Young MN. 2026 AHA/ACC/ACCP/ACEP/CHEST/SCAI/SHM/SIR/SVM/SVN Guideline for the Evaluation and Management of Acute Pulmonary Embolism in Adults: A Report of the American College of Cardiology/American Heart Association Joint Committee on Clinical Practice Guidelines. J Am Coll Cardiol. 2026 Feb 19:S0735-1097(25)10161-7. doi: 10.1016/j.jacc.2025.11.005. Epub ahead of print. PMID: 41712898.


Title: SIPE - A Review

Category: Critical Care

Keywords: immersion, SIPE, swimmer, swimming (PubMed Search)

Posted: 3/30/2026 by TJ Gregory, MD

Bottom Line: Swimming-Induced Pulmonary Edema (SIPE) AKA Immersion Pulmonary Edema is a rare, though life-threatening pathology associated with water-based activities, especially among athletes or military personnel. Caused by physiologic effects of immersion, not from aspiration/ingestion. Consider in any patient with respiratory distress or chest discomfort onset during water activities such as swimming, diving, etc. Diagnose with physical exam and POCUS. Manage supportively, potentially including positive pressure ventilation. Screen for alternative diagnoses.

See the link for more thorough review of assessment diagnostics, pathophysiology, pharmacological options, risk factors, and long-term considerations.

Show References

https://doi.org/10.1177/10806032251414379

Steins H. Swimming-Induced Pulmonary Edema: A Scoping Review and Analysis of Epidemiology, Pathophysiology, Diagnostics, Management, and Implications for Resource-Limited Care of Patients. Wilderness & Environmental Medicine. 2026;0(0). doi:10.1177/10806032251414379


Title: Bradycardia associated with intrabdominal hemorrhage

Category: Trauma

Keywords: Shock, bradycardia, Hemoperitoneum, hypotension, (PubMed Search)

Posted: 3/29/2026 by Robert Flint, MD (Updated: 9/17/2026)

Bradycardia accompanying hypotension can be found in spinal cord injury (loss of autonomic reflex), beta blocker and calcium channel blocker overdose, intrinsic cardiac electrophysiologic derangement, and, often forgotten, intrabdominal hemorrhage.  In the appropriate setting (blunt trauma, ruptured ectopic pregnancy), bradycardic hypotensive patients should be considered the same as tachycardic hypotensive patients and get a work up and treatment focused on Hemoperitoneum.

Show References

  1. Absence of a tachycardic response to intraperitoneal hemorrhage Stephen  L. Adams MD ?, James S. Greene MD †The Journal of Emergency Medicine Volume 4, Issue 5, 1986, Pages 383-389
  2. Howard S. Snyder, Stephen J. Dresnick, Lack of a tachycardic response to hypotension in penetrating abdominal injuries, The Journal of Emergency Medicine, Volume 7, Issue 4, 1989, Pages 335-339, ISSN 0736-4679, https://doi.org/10.1016/0736-4679(89)90294-1.
  3. Howard S. Snyder, Lack of a tachycardic response to hypotension with ruptured ectopic pregnancy,
    The American Journal of Emergency Medicine, Volume 8, Issue 1,1990,Pages 23-26, ISSN 0735-6757,
    https://doi.org/10.1016/0735-6757(90)90288-B.
  4. Rana MS, Khalid U, Law S. Paradoxical bradycardia in a patient with haemorrhagic shock secondary to blunt abdominal trauma. BMJ Case Rep. 2010 Oct 6;2010:bcr0420102872. doi: 10.1136/bcr.04.2010.2872. PMID: 22778107; PMCID: PMC3027800
  5. Jansen RP. Relative bradycardia: a sign of acute intraperitoneal bleeding. Aust N Z J Obstet Gynaecol. 1978 Aug;18(3):206-8. doi: 10.1111/j.1479-828x.1978.tb00051.x. PMID: 283785


Title: Ulnar sided hand and wrist pain in a baseball player

Category: Orthopedics

Posted: 3/28/2026 by Brian Corwell, MD

Question

https://prod-images-static.radiopaedia.org/images/52314030/8089eeb717fd6d20e108ec2e586ba4.jpg

Show Answer

Hamate Fractures:

Rare (2 to 4% of all carpal fractures)

Mechanism:  Usually a direct blow from a stick sport (bat, club or racket)

  • https://upload.orthobullets.com/topic/6035/images/hamate_baseball.jpg

Have increased suspicion in these athletes who present w/ ulnar sided wrist pain

Presents with hypothenar pain and pain with gripping activities

  • https://upload.orthobullets.com/topic/6035/images/hamate_golf.jpg

Fractures occur in two locations: the body and the hook of the hamate

  • The hook functions as a pulley for the flexor tendons of the ring and small fingers.
  • Fx of the body are more common than fx of the hook

On exam you will find:

  • Most patients complain of pain and tenderness on ulnar side of palm (localized over the hamate ) or on the dorsoulnar aspect of the wrist

Hook of Hamate Pull Test

Examiner places the wrist in full ulnar deviation with the fingers flexed.

Examiner pulls on the ring and pinky finger with the patient resisting the pull.

Positive test

  • Pain in area of the hook of hamate +/- radiating through palm.
  • https://wikism.org/w/images/thumb/e/ec/Hook_of_hamate_fracture_test.jpg/450px-Hook_of_hamate_fracture_test.jpg

Diagnosis:

  • PA and lateral views of the wrist may show a body fracture but will frequently MISS a fracture of the hook of the hamate. 
  • Most fractures can be diagnosed by plain films in the "Carpal tunnel view"
  • CT scan can also be used to see the fracture


Title: Room to improve goals of care conversations

Category: Geriatrics

Posted: 3/26/2026 by Robert Flint, MD

Using a database of 300,000 patients and applying a predictive measure for mortality, these authors found that patients over 66 with a high likelihood of 6 month mortality at the time of presentation were more likely to be admitted to an ICU when they presented to an ED. The authors conclude there is much work to be done regarding discussion of goals of care based on this information.

Show References

Adeyemi O, Hill J, Siman N, Goldfeld KS, Cuthel AM, Grudzen CR. Acute Care Use and Prognosis in Older Adults Presenting to the Emergency Department. J Pain Symptom Manage. 2025;69(6):559-568. doi:10.1016/j.jpainsymman.2025.01.006


Title: Safety Net EDs

Category: Administration

Keywords: safety net, uncompensated care, administration (PubMed Search)

Posted: 3/25/2026 by Mercedes Torres, MD (Updated: 9/17/2026)

Bottom Line: Safety-net hospitals are those that see a substantial share of uninsured, Medicaid, or low-income Medicare patients.  Their emergency departments (EDs) deliver disproportionally more undercompensated and uncompensated care, yet have similar operating costs as other EDs.  Authors convened a group of 15 administrators of academic safety net EDs to identify and
develop a consensus understanding of barriers to delivering optimal care.  See the link for details of their conclusions.

Show Additional Information
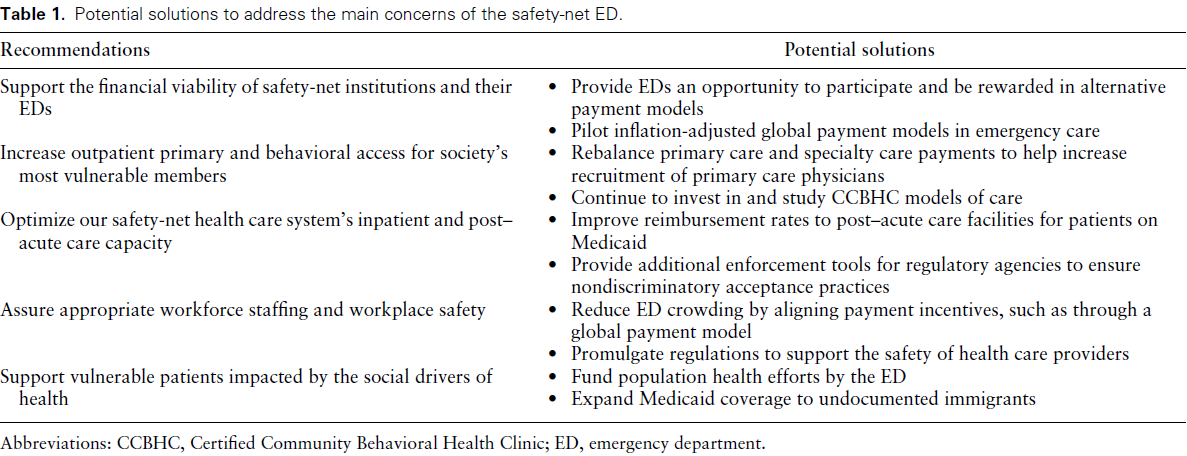
The 5 major calls to action specific to safety-net EDs identified by the group of content area experts
were as follows: 

(1) a need for financially aligned incentives

(2) a need for timely access to outpatient primary and behavioral care 

(3) a need to optimize our health care system’s in patient and post–acute care capacity

(4) a need to ensure appropriate workforce staffing and workplace safety

(5) a need to uniquely support vulnerable patients impacted by the social drivers of health.

Table 1 below shows potential solutions identified to address these concerns.

Show References

Yun BJ, Singh MK, Reznek MA, et al. Strengthening essential emergency departments: Transforming the safety net. Health Affairs Scholar, 2025, 3(3), doi.org/10.1093/haschl/qxaf044.


Title: Hot off the presses: Bullet Points for the 2026 Updated Surviving Sepsis Campaign Guidelines

Category: Critical Care

Keywords: Sepsis, Septic Shock, SSC, Surviving Sepsis Campaign (PubMed Search)

Posted: 3/24/2026 by Kami Windsor, MD (Updated: 3/24/2026)

Click the link for below to read the bulleted, abridged version of the Executive Summary of the Updated SSC Guidelines for Adults with Sepsis and Septic Shock 2026…

  • Strength of guidelines provided as conditional “suggestions” or strong “recommendations"
  • Amount of certainty given existing evidence (very low [VL], low, moderate)
    • Note “very low” certainty may simply indicate there isn't a study or any reliable data
  • Please refer to the article (linked in References) for given rationales from the SSC

Show Additional Information

New Statements for 2026:

  • Suggest using a standard sepsis screening tool over not  (VL cert)
  • Recommend initial MAP goal >65 over higher targets (moderate) 
    • Describes allowing a range within 5 mmHg… (so perhaps MAP 60-70 mmHg?)
  • For adults 65yrs+ still suggest MAP 60-65mmHg over higher ranges (low)
  • For likely septic shock if prehospital time is likely to be >60 min, suggests prehospital abx (VL)
    • Commented that this should only be w/ use of sepsis screening tool
  • Suggest empiric abx without anaerobic coverage unless there are risk factors for anaerobic infection (VL)
    • Okay to use ones with anaerobic coverage (such as piperacillin-tazobactam) if otherwise required for resistant infections
    • Risk factors listed: intraabdominal or gyn/OB source, necrotizing STI, HEENT infection, CNS abscess/empyema
  • Suggest empiric abx WITH anaerobic coverage if risk factors are there (VL)
  • Suggest selective decontamination of digestive tract  in mechanically-ventilated adults in units with low prevalence of antimicrobial resistance (moderate)
  • After acute resuscitation phase, ‘suggest” using active fluid removal (diuretics, dialysis, etc.) (VL)

Changes in Suggestion/Recommendations from 2021:

  • Suggest against using empiric antifungal (low certainty) instead of using empiric antifungal for those at risk
  • Suggest using either invasive or NIBP monitoring (VL) instead of recommending invasive monitoring in patients with septic shock
    • Still recommends invasive for intermediate-to-high dose pressors, escalating or multiple pressors, needing frequent  ABGs, or inconsistent NIBP measurements
  • Suggest using crystalloids alone over crystalloids with supplemental albumin (moderate) instead of conditional recommendation for albumin if large volumes of crystalloid given
    • Notes albumin may be appropriate for pts who have received a lot of crystalloid already or have cirrhosis, and to avoid in TBI patients

Changes in Strength of Recommendation or Evidence Certainty since 2021:

Upgrades

  • “Strong” recommendation (from “conditional”) for prolonged infusion maintenance beta-lactams after initial loading dose (moderate certainty)
  • “Strong” recommendation to deescalate abx to appropriate narrower therapy once bacteria/susceptibility profile is available (from “conditional”; VL)
  • “Moderate” certainty evidence for suggestion to use balanced crystalloids over 0.9% saline (from "low”)
  • “Low” certainty evidence suggestion to use dynamic measures (response to passive leg raise or test bolus using stroke volume, stroke volume variation, pulse pressure, or pulse pressure variation) to guide initial fluid resuscitation over physical exam or static measures alone (from “very low”)

Downgrades

  • “Conditional” suggestion (from recommendation) to use NE (norepinephrine) first over vasopressin (low cert) or Ang II (VL cert)
    • Strong rec to use NE first over dopamine/epi/selepressin still in place
  • “Very low” evidence for suggestion to add Epi if MAP inadequate despite NE and vasopressin (from “low”)
  • “Very low” certainty of evidence for suggestion to add dobutamine to NE, or use epinephrine alone, for pts with persistent shock & cardiac dysfunction despite adequate fluid resus and appropriate MAP
    • no guidance on dobutamine vs milirinone
  • “Low” certainty of evidence for suggestion for IV corticosteroids in septic shock (from “moderate”)

Otherwise the same:

  • Treat sepsis / septic shock immediately and as emergencies
  • Suggest at least 30mL/kg IV crystalloid in the first 3 hours for sepsis-related hypoperfusion/shock (low certainty) using adjusted or ideal BW in patients with BMI>30. 
  • Recommend abx within 1hr of recognition for probable/definite sepsis and for possible/definite septic shock (VL)
  • Suggest a time-limited course of investigation for possible sepsis and if infection likely, abx within 3 hrs (VL)

Show References

Prescott HC, Antonelli M, Alhazzani W, et al. Executive Summary: Surviving Sepsis Campaign: International Guidelines for Management of Sepsis and Septic Shock 2026. Crit Care Med. 2026 Mar 23. doi: 10.1097/CCM.0000000000007089. Epub ahead of print.


Title: Test Now, Treat Now? Disparities in Empiric STI Treatment by Sex

Category: Infectious Disease

Keywords: STI, empiric treatment, sex disparity (PubMed Search)

Posted: 3/23/2026 by Lena Carleton, MD (Updated: 3/23/2026)

Bottom Line: Among adult ED patients tested for gonorrhea and chlamydia, empiric treatment often does not align with confirmed infection. There are also notable sex disparities; in this study, females with confirmed infection were ~3.5 times more likely than males to not receive empiric treatment.

Show Additional Information

Empiric treatment for gonorrhea (GC) and chlamydia trachomatis (CT) is common in the emergency department due to delayed test results. This systematic review and meta-analysis evaluated how well empiric treatment aligns with laboratory-confirmed infections, with a focus on overtreatment, undertreatment, and sex differences.

The authors included U.S.-based ED studies published between January 2010 and January 2025 (excluding pediatric EDs). Nineteen studies with 32,593 patients met the inclusion criteria. Although GC and CT were initially analyzed separately, they were combined due to inconsistent reporting.

Overall, 14% of tested patients had confirmed GC/CT (11% of females vs. 25% of males). Empiric treatment was given to 46% of patients, less often in females (31%) than in males (73%). Among patients with confirmed infection, 39% were not empirically treated, with a markedly higher rate in females (52%) compared to males (15%), suggesting females were ~3.5 times more likely to be undertreated.

Potential explanations include higher rates of symptomatic disease in males and broader testing in females with abdominal or pelvic complaints, which lowers test positivity rates. Bias, implicit or explicit, may also contribute.

Overall, there is significant discordance between empiric treatment and confirmed infection, with notable sex disparities. At the bedside, shared decision-making around empiric treatment is essential. At a systems level, EDs should ensure reliable follow-up processes to notify and treat patients who test positive after discharge.

Show References

Solnick RE, Patel R, Chang E, et al. Sex disparities in chlamydia and gonorrhea treatment in U.S. adult emergency departments: A systematic review and meta-analysis. Acad Emerg Med. 2025; 32: 1003-1016. doi:10.1111/acem.70070


Title: Low titer O whole blood use

Category: Trauma

Keywords: Whole blood, trauma center level (PubMed Search)

Posted: 3/22/2026 by Robert Flint, MD (Updated: 9/17/2026)

Looking at a national database, this study concluded the use of low titer O whole blood during trauma resuscitations  was increasing at level one centers but not at level 2 and 3 centers. Is this a representation of the national blood supply as whole blood is harder to stock? We need to understand this trend to assure equal and appropriate care to trauma patients across the country.

Show References

TransfusionEarly View

LETTER TO THE EDITOR

Trends in low titer group O whole blood use among United States trauma centers: An update from a national trauma registry from 2020 to 2024

Steven G. Schauer, Mark H. Yazer

First published: 01 February 2026

https://doi.org/10.1111/trf.70096


Title: Treatment concerns of Muslim patients with diabetes during Ramadan

Category: Administration

Keywords: Ramadan, Muslim, diabetes (PubMed Search)

Posted: 3/21/2026 by Hanna Hussein, MD (Updated: 9/17/2026)

Educational Pearls for the ED:

Many Muslim patients with diabetes will fast despite medical advice. Studies show a significant number continue fasting even when they are considered high risk.

Key medical risks during Ramadan fasting include:

- Hypoglycemia

- Hyperglycemia and diabetic ketoacidosis

- Dehydration

- Medication nonadherence or altered dosing schedules

Show Additional Information

This article discusses the ethical and clinical challenges that arise when Muslim patients with diabetes choose to fast during Ramadan. During this month, fasting from dawn to sunset involves abstaining from food, drink, and oral medications, which can complicate chronic disease management and increase risks such as hypoglycemia, hyperglycemia, dehydration, and medication nonadherence. Despite these risks, many patients still opt to fast due to strong religious and cultural motivations. The authors highlight gaps in physician–patient communication, including limited counseling on medication adjustments and risk stratification before Ramadan, as well as physicians’ lack of familiarity with the religious significance of fasting. Ethically, this situation reflects the balance between patient autonomy and physician beneficence. Rather than simply telling patients not to fast, the authors recommend culturally sensitive counseling, shared decision-making, and proactive pre-Ramadan planning to promote safer fasting practices while respecting patients’ beliefs.

Islam provides exemptions from fasting for illness, including diabetes in many cases. However, patients may still choose to fast for personal or cultural reasons. Avoid framing the discussion as “you cannot fast.” A shared decision-making approach that recognizes the religious importance of fasting is generally more effective. Pre-Ramadan counseling is essential. Ideally, patients should be seen before Ramadan to discuss risk stratification, medication adjustments, hydration strategies, and when to break the fast. In the ED, consider fasting status when evaluating diabetic patients presenting with hypoglycemia, hyperglycemia, or dehydration during Ramadan. Cultural competence is important. Even a brief acknowledgment of Ramadan’s significance can help build trust and improve adherence to medical recommendations.

Show References

Ethical conflicts in the treatment of fasting Muslim patients with diabetes during Ramadan
Ilhan Ilkilic · Hakan Ertin

Med Health Care and Philos (2017) 20:561–570
DOI 10.1007/s11019-017-9777-y


Previous  |  1 |  2 |  3 |  4 |  5 |  6 |  7 |  8 |  9 |  10 |  11 |  12 |  ... |  239 |  Next
University of Maryland School of Medicine logo
  • Departments
  • Programs
  • Research Centers
  • Institutes
  • Graduate Education
  • CIBR Cores
  • Offices of the Dean
    • University of Maryland, Baltimore
    • University of Maryland Medical Center
    • Medical Alumni Association of the University of Maryland
    • Health Sciences and Human Services Library
University of Maryland School of Medicine
655 W. Baltimore Street
Baltimore, MD 21201
Contact Us

© University of Maryland School of Medicine

    • Webmaster
    • Web Accessibility
    • Site Index
    • UMB Hotline
    • Employment
    • Map