
Consider esmolol IV 500 mcg/kg loading dose followed by a continuous infusion of 0-100 mcg/kg/min for patients in refractory ventricular fibrillation
Show Additional Information
Show References
Misclassification of adverse drug effects as allergy is commonly encountered in clinical practice and can lead to use of suboptimal alternate medications which are often less effective.
- Nomenclature surrounding drug safety needs to be clear and unambiguous to avoid confusion.
- Adverse Drug Effect (ADE) = All drug induced disease. Majority are predictable based on drug's known pharmacology. Include harm related to medication errors and drug/food interactions.
- Adverse Drug Reaction (ADR) = Noxious or unintended reaction to a drug that is administered at therapeutic doses during normal use. Divided into predictable (majority 75-80%), related to pharmacologic actions of the drug in otherwise normal individuals) and unpredictable reactions (related to individual’s immunological response).
- "Drug allergies" are relatively uncommon with cited incidence of 10%. Immunologically mediated reactions (type I to IV) to a pharmaceutical and/or formulation (excipient) in a sensitized person. They are dose independent and unrelated to pharmacological action of the drug. Most commonly, IgE-mediated type I (immediate) reactions caused by rapid release of vasoactive mediators from mast cells and peripheral basophils causing generalized reaction including urticaria, angioedema, stridor, wheezing, and cardiovascular collapse.
- The skin is the most frequently and notably affected by drug induced allergic reactions.
- Antibiotics, particuarly Beta-Lactams, are the most important cause of immediate hypersensitivity reactions. Approximately 10% of patients report a history of penicillin allergy, however after complete evaluation, up to 90% of these individuals are able to tolerate penicillin and are designated as having “penicillin allergy” unnecessarily.
- Pseudoallergy can occur with opioids due to histamine release. Codeine and morphine are most commonly associated with pseudoallergy. Coadministration of an antihistamine or use of a semi or synthethic opioid (Fentanyl, hydromorphone) can prevent this reaction.
Show Additional Information
Show References
The World Health Organization announced on November 18th, 2016 that the Zika virus and associated consequences will no longer Public Health Emergency of International Concern. This changes the originally recommendation in February 2016.
However, Zika remains a “significant enduring public health challenge requiring intense action”. The consequences of the disease remains significant, especially for pregnant women and infants.
Show Additional Information
Show References
--In this study, PE was diagnosed in ~17% of patients hospitalized for syncope (though this represents only ~4%% of patients presenting to the ED with syncope).
--Patients with PE were more likely to have tachypnea, tachycardia, relative hypotension, signs of DVT, and active cancer -- take a good history and do a good physical exam!
--Consider risk stratifying (Wells/Geneva) and/or performing a D-dimer (i.e "rule out" PE) on your syncope patients, particularly when no alternative diagnosis is apparent.
Show Additional Information
Show References
Incidence and Cost of Ankle Sprains US Emergency Departments
In a sample of 225,114 ED patients with ankle sprains:
Lateral ankle sprains represent the vast majority of all ankle sprains (91%).
Lateral ankle sprains incur greater ED charges than medial sprains ($1008 vs. $914).
Lateral ankle sprains were more likely to have associated pain in the limb, sprain of the foot and abrasions of the hip/leg than medial sprains.
Medial sprains were more likely to include imaging.
Hospitalizations were more likely with high ankle sprains than lateral sprains.
There is a higher incidence of ankle sprains in younger patients (≤25 years) and in female patients (57%).
Show References
Which first-line vasoactive drug is the best choice for children with fluid-refractory septic shock? A prospective, randomized, blinded study of 120 children compared dopamine versus epinephrine in attempts to answer this debated question in the current guidelines for pediatric sepsis.
Bottom line: Dopamine was associated with an increased risk of death and healthcare–associated infection. Early administration of peripheral or intraosseous epinephrine was associated with increased survival in this population.
Show Additional Information
Show References
What Matters in Cardiac Arrest?
- Approximately 500,000 adults suffer sudden cardiac arrest each year in the United States.
- The most important components of cardiac arrest care that have been shown to improve outcomes are:
- High-quality CPR with little to no interruptions
- Defibrillation for ventricular arrhythmias
- Optimal post-arrest care
- Target an SpO2 of 94-98%
- Target an ETCO2 of 35-40 mm Hg (PaCO2 of 40-45 mm Hg)
- Targeted temperature management
- Early cardiac catheterization
Show References
Question
A 15 months old male with no past medical history, presenting with two days of decreased oral intake and decreased urine output. The exam was notable for minimal tenderness of abdomen. During an oral fluid challenge in the ED, the patient had a single episode of bilious vomiting. The ED physician ordered an ultrasound study and the results are shown below. What is the diagnosis?

Show Answer
Show References
Using 1.5 mg/kg or 2 mg/kg of IV ketamine led to less redosing compared to using 1 mg/kg IV.
Show Additional Information
Show References
Recently a review paper was published regarding the duration of observation in heroin overdose patients who received naloxone.
It made several conclusions regarding heroin overdose:
- Treat (naloxone) and release in a prehospital setting may be safe.
- Short observation period (minimum of 1 hour) for heroin OD patients who were treated in the ED may be safe.
- Bystander and first responder naloxone administration is effective and safe.
It should be pointed out that this is a review paper of limited number of articles with variable quality. Additionally, the clinical history of “heroin use” may be unreliable as fentanyl and novel synthetic opioids are also sold as “heroin.” Providers should exercise appropriate clinical judgement when caring for these patients.
Show Additional Information
Show References
It is well documented that when left to our own respiratory devices we will consistently over-ventilate patients presenting in cardiac arrest (1). A simple and effective method of preventing these overzealous tendencies is the utilization of a ventilator in place of a BVM. The ventilator is not typically used during cardiac arrest resuscitation because the high peak-pressures generated when chest compressions are being performed cause the ventilator to terminate the breath prior to the delivery of the intended tidal volume. This can easily be overcome by turning the peak-pressure alarm to its maximum setting. A number of studies have demonstrated the feasibility of this technique, most recently a cohort in published in Resuscitation by Chalkias et al (2). The 2010 European Resuscitation Council guidelines recommend a volume control mode targeting tidal volumes of 6-7 mL/kg and a respiratory rate of 10 breaths/minute (3).
It is well documented that when left to our own respiratory devices we will consistently over-ventilate patients presenting in cardiac arrest (1). A simple and effective method of preventing these overzealous tendencies is the utilization of a ventilator in place of a BVM. The ventilator is not typically used during cardiac arrest resuscitation because the high peak-pressures generated when chest compressions are being performed cause the ventilator to terminate the breath prior to the delivery of the intended tidal volume. This can easily be overcome by turning the peak-pressure alarm to its maximum setting. A number of studies have demonstrated the feasibility of this technique, most recently a cohort in published in Resuscitation by Chalkias et al (2). The 2010 European Resuscitation Council guidelines recommend a volume control mode at 6-7 mL/kg and 10 breaths/minute (3).
Show References
Question
https://images.radiopaedia.org/images/3173801/1ee24da1a6fe907a27d2bf20481174.jpg

Young toddler presents with left lower leg pain. What is the diagnosis??
Show Answer

Question
Patient found pulseless after submersion in water for 20 minutes. After ROSC, patient’s GCS was 3 and pupils are dilated and nonreactive.

Show Answer
Show References
It's Election Day in the US, so here are some interesting facts about Presidential causes of death:
George Washington likely died from epiglottitis on 12/14/1799
- However, "iatrogenic" should also be listed on his cause of death
- Washington was blood let for almost 2.4L of blood!!!
- He also received an enema and multiple "blistering" treatments to draw the evil humors out of his throat
- He died before his fourth doctor, who planned to perform a tracheostomy, could arrive
CLICK BELOW FOR MORE INTERESTING FACTS!
Show Additional Information
Question
8 year-old female with no PMH who presents with concerns for "purple patches" popping up on her arm for 2-3 days. Stated that one appeared and then, the other one appeared 12 hours later. She denied any trauma whatsoever, history of easy bleeding/bruising and did feel safe at home. The rest of the review of systems was negative.
Patient said there was mild pain when the area was touched. The rest of the physical examination was normal.
What's the diagnosis? (Image below)

Show Answer
Show References
Do you have a patient with renal insufficiency who is in need of an anticoagulation bridge to warfarin? Subcutaneous unfractionated heparin (UFH) as an initial dose of 333 Units/kg subcutaneously followed by a fixed dose of 250 Units/kg (actual body weight) every 12 hours may be an alternative to admission for heparin infusion with monitoring.
Show Additional Information
Show References
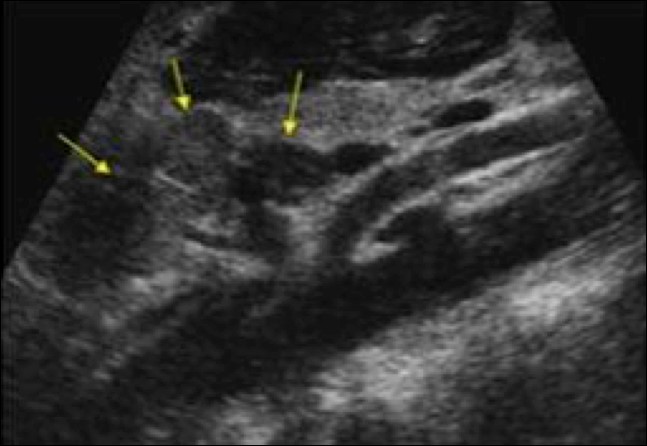
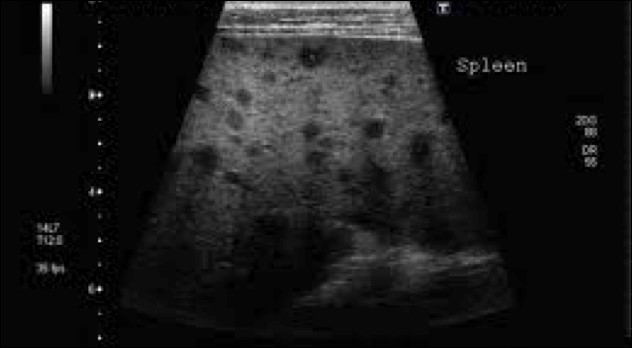
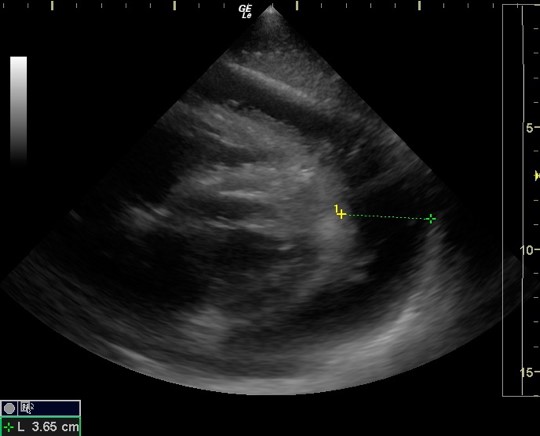
As noted in a previous post, the FASH exam is the Focused Assessment with Sonography for HIV/TB. Below are typical ultrasound images of a positive FASH exam.
Peri-aortic lymph nodes- Multiple enlarged nodes, 97.1% specific for TB
Splenic lesions – multiple ‘punched out’ lesions
The effusions often have fibrous stranding
Submitted by Dr. Laura Diegelmann
Show Additional Information
Show References
Dynamic LVOT Obstruction
- Recent literature has indicated that dynamic LVOT obstruction can occur in critically ill patients without hypertrophic cardiomyopathy. In fact, a recent study found that this condition may be present in many patients with septic shock.
- Risk factors for LVOT obstruction include any condition that decreases afterload, decreases preload, or increases heart rate.
- Consider LVOT obstruction when your ultrasound demonstrates close approximation of the lateral wall and septum plus systolic anterior motion of the anterior mitral leaflet.
- The treatment of patients with dynamic LVOT obstruction includes:
- Increasing preload with aggressive IVFs
- Increasing afterload (phenylephrine may be a good choice)
- Avoiding inotropes
- Decreasing heart rate (often with esmolol)
Show References
Question
30 year old female presents with a painful finger for 1 week. Finger exam showed the following. What is the diagnosis ?
