
Search
Subscribe to daily UMEM Pearls (FREE!) via:
221-240 of 335 results by Robert Flint
192 trauma patients who were receiving pre-hospital fentanyl for moderate to severe pain were randomized to placebo or intranasal 50 mg ketamine as an adjunct for pain control. There was no difference between the two groups in decrease in pain scale.
The authors concluded: “In our sample, we did not detect an analgesic benefit of adding 50 mg intranasal ketamine to fentanyl in out-of-hospital trauma patients.”
Show References
The systematic review of presyncope literature found that presyncope should be treated the same as syncope in terms of work up and disposition.
“In conclusion, the prevalence of short-term serious outcomes among ED patients with presyncope ranges from one in four to one in 20, with arrhythmia being the most common serious outcome. Our review indicates that presyncope may carry a similar risk to syncope, and hence, the same level of caution should be exercised for ED presyncope management as that of ED syncope.”
Show References
Two recommendations from the recent GRACE 4 publication in Academic Emergency Medicine to consider:
1. Use phenobarbital along with benzodiazepines in patients with moderate to severe alcohol withdrawal. The evidence isn’t robust but is positive when compared to benzos alone.
2. Adults with alcohol use disorder can benefit from anti-craving medications such as naloxone and gabapentin at time of discharge.
Show References
A prospective European study of patients over age 65 presenting with a ground level fall obtained troponin levels to ascertain if myocardial infarction was a cause of the ground level fall. Troponin levels were elevated in a majority of patients however only 0.5% were defined as having a myocardial infarction. Of the 3% who died within 1 year, troponin was found to be higher than those that survived the one-year study period. The authors concluded “Our data do not support the opinion that falls may be a common presenting feature of MI. We discourage routine troponin testing in this population. However, hs-cTnT and hs-cTnI were both found to have prognostic properties for mortality prediction up to 1?year.”
Show References
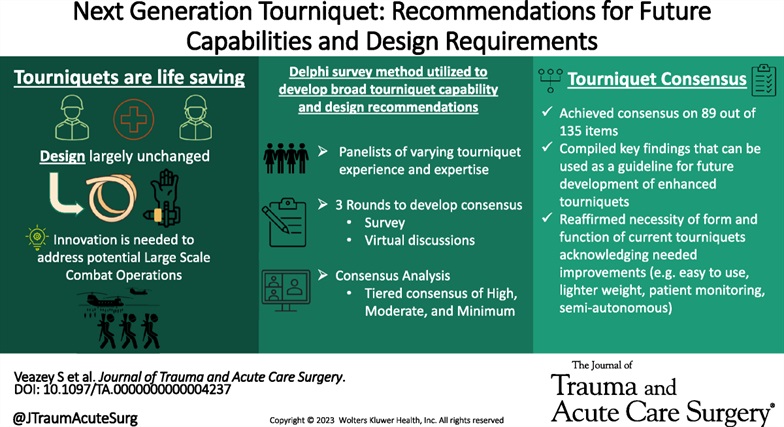
Appropriately, a great deal of time and energy is being expended to educate on the use of tourniquets to prevent mass hemorrhage. Are the current generation of tourniquets the best that we can have? These authors performed a Delphi study to assess needs with tourniquet design.
They concluded the next generation of tourniquets should have the following: “Capable of being used longer than 2 hours, applied and monitored by anyone, data displays, semiautomated capabilities with inherent overrides, automated monitoring with notifications and alerts, and provide recommended actions.”
Show References
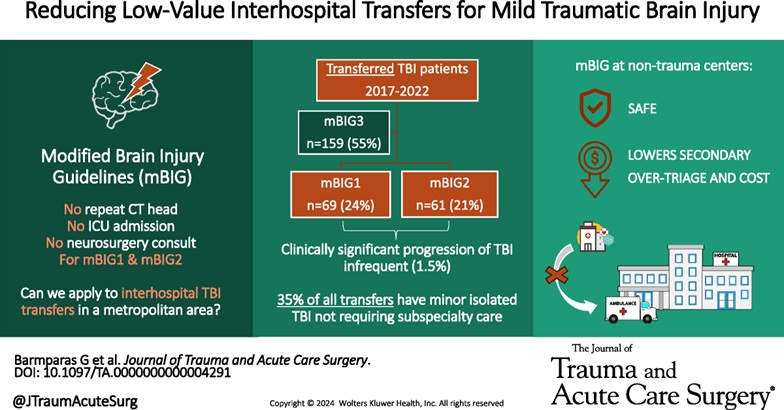
This study used the modified Brain injury Guidelines retrospectively to assess whether the guidelines would have saved transfers to their level one facility safely. They concluded the guidelines would have effectively prevented unnecessary mBIG 1 and mBIG2 transfers with no patient harm.
TABLE 1 - Modified Brain Injury Guidelines Radiologic Stratification, as per Kahn et al.
| mBIG 1 | mBIG 2 | mBIG 3 | |
|---|---|---|---|
| Skull fracture | No | Non-displaced | Displaced |
| SDH | ?4 mm | 4–7.9 mm | ?8 mm |
| EDH | No | No | Yes |
| SAH | ?3 sulci and <1 mm | Single hemisphere or 1–3 mm | Bihemisphere or >3 mm |
| IVH | No | No | Yes |
| IPH | ?4 mm | 4–7.9 mm | ?8 mm or multiple |
EDH, epidural hematoma; IPH, intraparenchymal hemorrhage; IVH, intraventricular hemorrhage; SAH, subarachnoid hemorrhage.
Show References
In this Scandinavian study looking at 2,362 head injury patients on oral anticoagulants, the authors found only 5 cases of delayed hemorrhage and none of the five underwent neurosurgery. The authors concluded:
“In patients with head trauma, on oral anticoagulation, the incidence of clinically relevant delayed intracranial hemorrhage was found to be less than one in a thousand, with detection occurring four days or later after initial presentation.”
It would appear based on this study and others that it is safe to discharge these patients with a normal head CT and giving strict return precautions for headache, nausea, vomiting or other changes.
Show References
This Delphi study and companion editorial highlight current thought on frailty screen in emergency department patients. Key takeaways are:
- Those with a high degree of frailty may have different care goals and needs than those with lower frailty.
2. Screening should include functional status in the past 2-4 weeks.
3. Screening should include functional ability, cognition, mobility, medication use and social situation.
4. Screening is practical and can be completed quickly.
5. Screening should occur in the first 4 hours of an ED visit.
6. ED protocols designed for streamlined, single problem focused visits won’t work well for those with a high degree of frailty.
Emergency departments should be instituting procedures that incorporate screening older patients for frailty. These references are a good starting point.
Show References
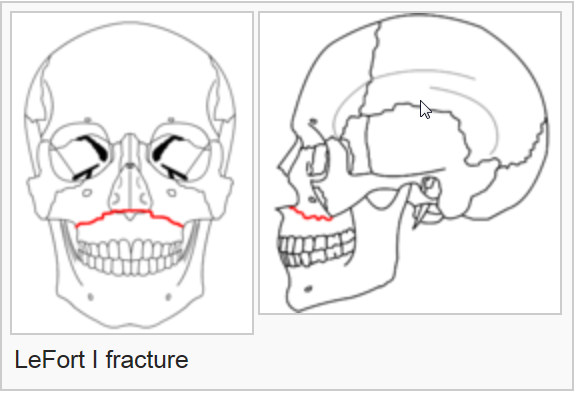
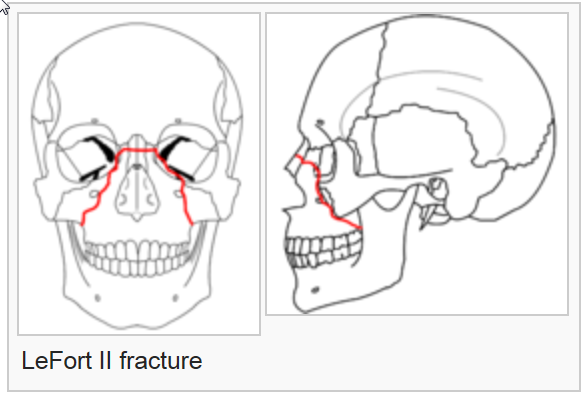
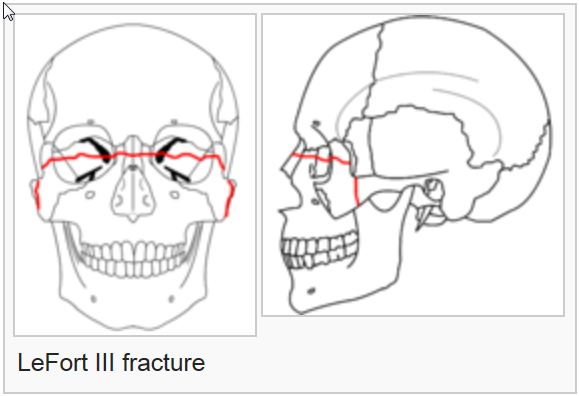
On exam, assess for facial instability and airway patency. CT scan is the imaging of choice. The higher the number, the more complex the fracture, the more unstable and the more difficult the airway managment will be. Look for open lacerations or blood in the sinuses and treat with antibiotics if these are found. Consult ENT or plastics urgently for further management.
The reference is a nice review of these fractures
Show References
This very small study looked at the utility of using IV contrast media to enhance abdominal sonography in identifying injuries in blunt abdominal trauma patients. The comparison was CT scanning of the abdomen to identify injuries. The study concluded:
“With the addition of contrast and careful inspection of solid organs, abdominal sonography with contrast performed by the emergency physician improves the ability to rule out traumatic findings on abdominal CT. CEUS performed by emergency physicians may miss injuries, especially in the absence of free fluid, in cases of low-grade injuries, simultaneous injuries, or poor-quality examinations.”
To me, this is a limited study and the technique is not ready for wide spread use but further study is warranted.
Show References
In this podcast, the concept of vasopressor use in hemorrhagic shock is discussed. Key take away points:
- US and UK literature is much less supportive of vasopressor use in hemorrhagic shock than continental European literature.
- Concept is while filling the tank with blood, getting some squeeze in the venous system to keep it circulating.
- If a young trauma patient has cool extremities, they are already vasogenic and unlikely to benefit from vasopressors. Warm extremities mean they may benefit from vasopressors.
- Norepinephrine is the drug of choice. Aim for a maintenance dose of 3-5 mcg/min and no need to titrate because you are not looking for arterial constriction, just venous tone.
- Low dose Vasopressin drip may be beneficial as well, however more literature is needed.
- Blood is still the answer in these patients! Vasopressors are an adjunct to creating a balanced resuscitation.
Show References
This retrospective study looked at patients diagnosed with urinary tract infections receiving an IV dose of antibiotics prior to discharge and compared ED length of stay and return visit rate. They found:
“Parenteral antibiotic administration in the ED was associated with a 60-minute increase in ED LOS compared with those who received an oral antibiotic (P < 0.001) and a 30-minute increase in ED LOS compared with no antibiotic (P < 0.001). No differences were observed in revisits to the ED at 72 hours”
Appears no benefit to the practice of IV antibiotics prior to discharge in UTI patients.
Show References
Hemodynamic instability in trauma patients is most often associated with hemorrhagic shock, however, there is an entity known as brain injury associated shock (BIAS). BIAS is thought to be associated with catecholamine surges secondary to brain injury. BIAS is found in both isolated head injury pts as well as multi-trauma patients. Studies have identified BIAS in 13% of adult trauma patients and up to 40% of pediatric major trauma patients.
We know hypotension in brain injury worsens outcome. We should assume hemorrhagic etiology until we prove otherwise. Once we suspect BIAS and have excluded hemorrhagic etiology our strategy should switch to blood pressure support using non-blood product management.
Show References
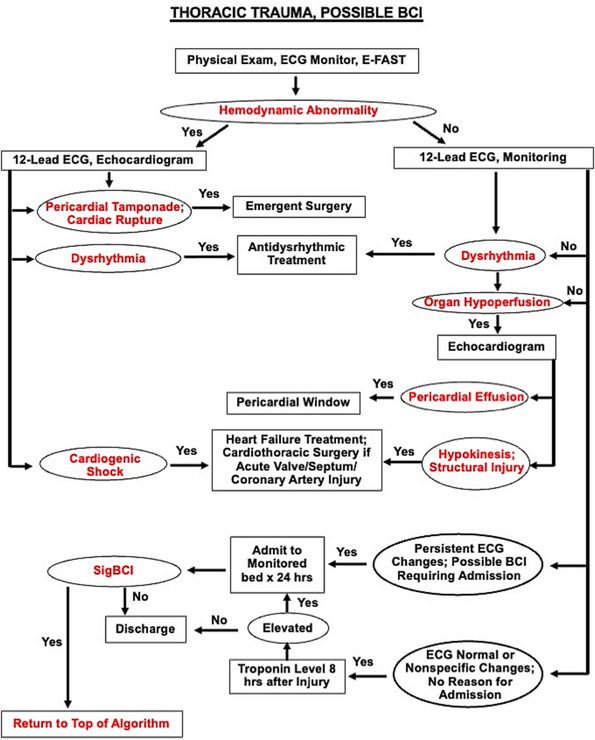
Blunt Cardiac Injury is a continuum from asymptomatic, not clinically relevant to catastrophic, life ending disease . Consider blunt cardiac injury in patients with significant force to the chest wall or sudden deceleration injuries (motor vehicle crashes, motorcycle crashes, falls from height etc.). This algorithm is helpful when working up patients suspected of having significant blunt cardiac injury.
Show References
In a cohort of 93,512 ED patients discharged with a diagnosis of hypertension there were 4400 who received a prescription for antihypertensives. The group receiving a prescription had fewer 30 day revisits and adverse events such as MI, CHF, etc.
Previous study’s have found it is safe to prescribe antihypertensives from the ED.
This study is limited by the fact it is not a randomized control trial and there are many variables as to why the select patients received prescriptions
The authors conclude: “Prescription antihypertensive therapy for discharged ED patients is associated with a 30-day decrease in severe adverse events and ED revisit rate.”
Show References
A small study retrospectively looking at recorded calls to a level 1 trauma center transfer line specifically looking at patients who died or were discharged to hospice without surgical intervention found only 10% had goals of care discussed prior to transfer. Most were brain hemorrhage patients.
As a transferring facility, clearly outlining goals of care and addressing futility of care can have a major impact on trauma transfers and the cost and family burden associated with transfers.
Show References
PECARN has a decision tool to identify blunt trauma patients under age 18 who are low probability for important intra-abdominal injuries. The questions to ask are:
- Evidence of abdominal wall trauma/seatbelt sign
- GCS <14 with abdominal trauma
- Abdominal tenderness
- >1 of thoracic wall trauma, vomiting, complaint of abdominal pain, decreased breath sounds
Answering no to all yields <0.1% chance of intra-abdominal trauma requiring intervention. (See MedCalc link for other calculations)
A prospective validation study in the Lancet yielded 100% sensitivity and negative predictive value in 7542 patients under age 18
This tool can likely be used to guide imaging choices in pediatric blunt abdominal trauma patients
Show References
This study looked at survival pre and post implementation of an airway guideline for prehospital traumatic brain injury (TBI) patients who received positive pressure airway interventions. The guideline “focused on the avoidance and aggressive treatment of hypotension and 3 airway-related goals: (1) prevention or treatment of hypoxia through early, high-flow oxygen administration; (2) airway interventions to optimize oxygenation or ventilation when high-flow oxygen was insufficient; and (3) prevention of hyperventilation or hypocapnia by using ventilation adjuncts (ie, rate timers, flow-controlled ventilation bags, end-tidal carbon dioxide monitoring).”
Post implementation, survival to admission increased in all severity levels of TBI and in the most severely injured, survival to discharge improved.
Useful for those involved in prehospital education and as a reminder for in hospital airway management in TBI patients.
Show References
Traditionally, a systolic blood pressure (SBP) of 90 has been used as a marker of severe illness in trauma patients. This study looked at a large database and found shock index (SI) and systolic blood pressure were the best predictors of early mortality in trauma patients.
They found:
prehospital SI 0.9 and SBP 110,
ED SI 0.9 and SBP 112,
and
in elderly
prehospital SI 0.8 SBP 116
ED SI 0.8 SBP 121
were the cutoffs to predict early mortality.
We should rethink our protocols and approach to trauma patients using a higher systolic blood pressure than 90. Also note elderly had a different number than younger trauma patients.