
Search
Subscribe to daily UMEM Pearls (FREE!) via:
1-20 of 335 results by Robert Flint
This meta analysis looking at the literature regarding fall prevention measures in patients over 60 years old found a significant amount of heterogeneity in the literature and no proof that fall prevention measures had any impact on 3,6,12 month mortality or re-hospitalization. More work is needed in this area to know better what, if anything, can impact this important patient safety measure.
Show References
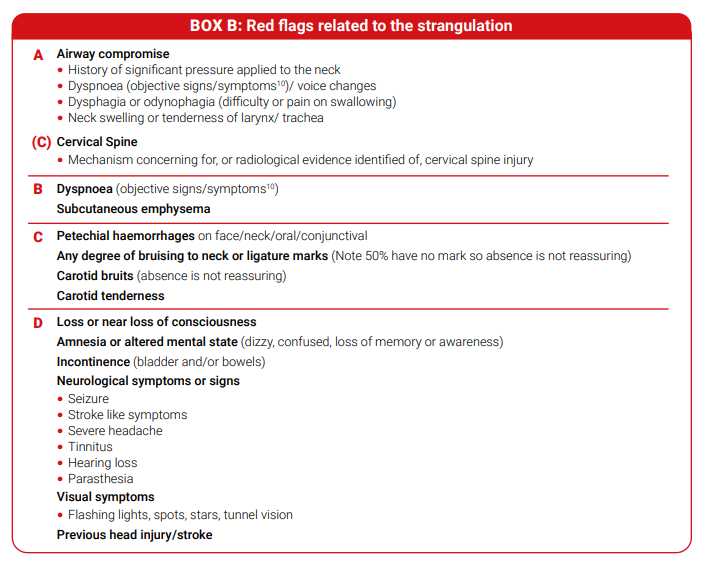
Evaluation of non-fatal strangulation patients with these signs is a CT angiogram of the neck.
Also note that this is a common finding in domestic violence and is a predictor of future injury and death from this partner.
Show References
This South African study looked at 194 hanging or strangulation injury patients and found that no clinical feature excluded blunt cerebral vascular injury (BCVI) in these patients. Nearly 5% of these patients had BCVI. The authors concluded the only safe way to exclude BCVI in post hanging/strangulation injury was CT angiography of the neck.
Show References
How well do the Denver and Memphis screening criteria identify blunt cerebral vascular injury?
From 2021:
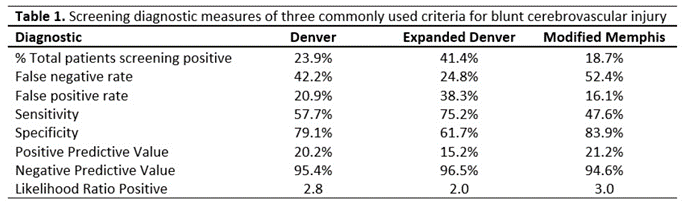
Not very well! Blunt injury to the head and neck may be enough to prompt you to order a CTA of the neck.
Click to see Memphis criteria which overlap Denver
Show Additional Information
Show References
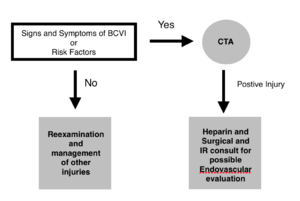
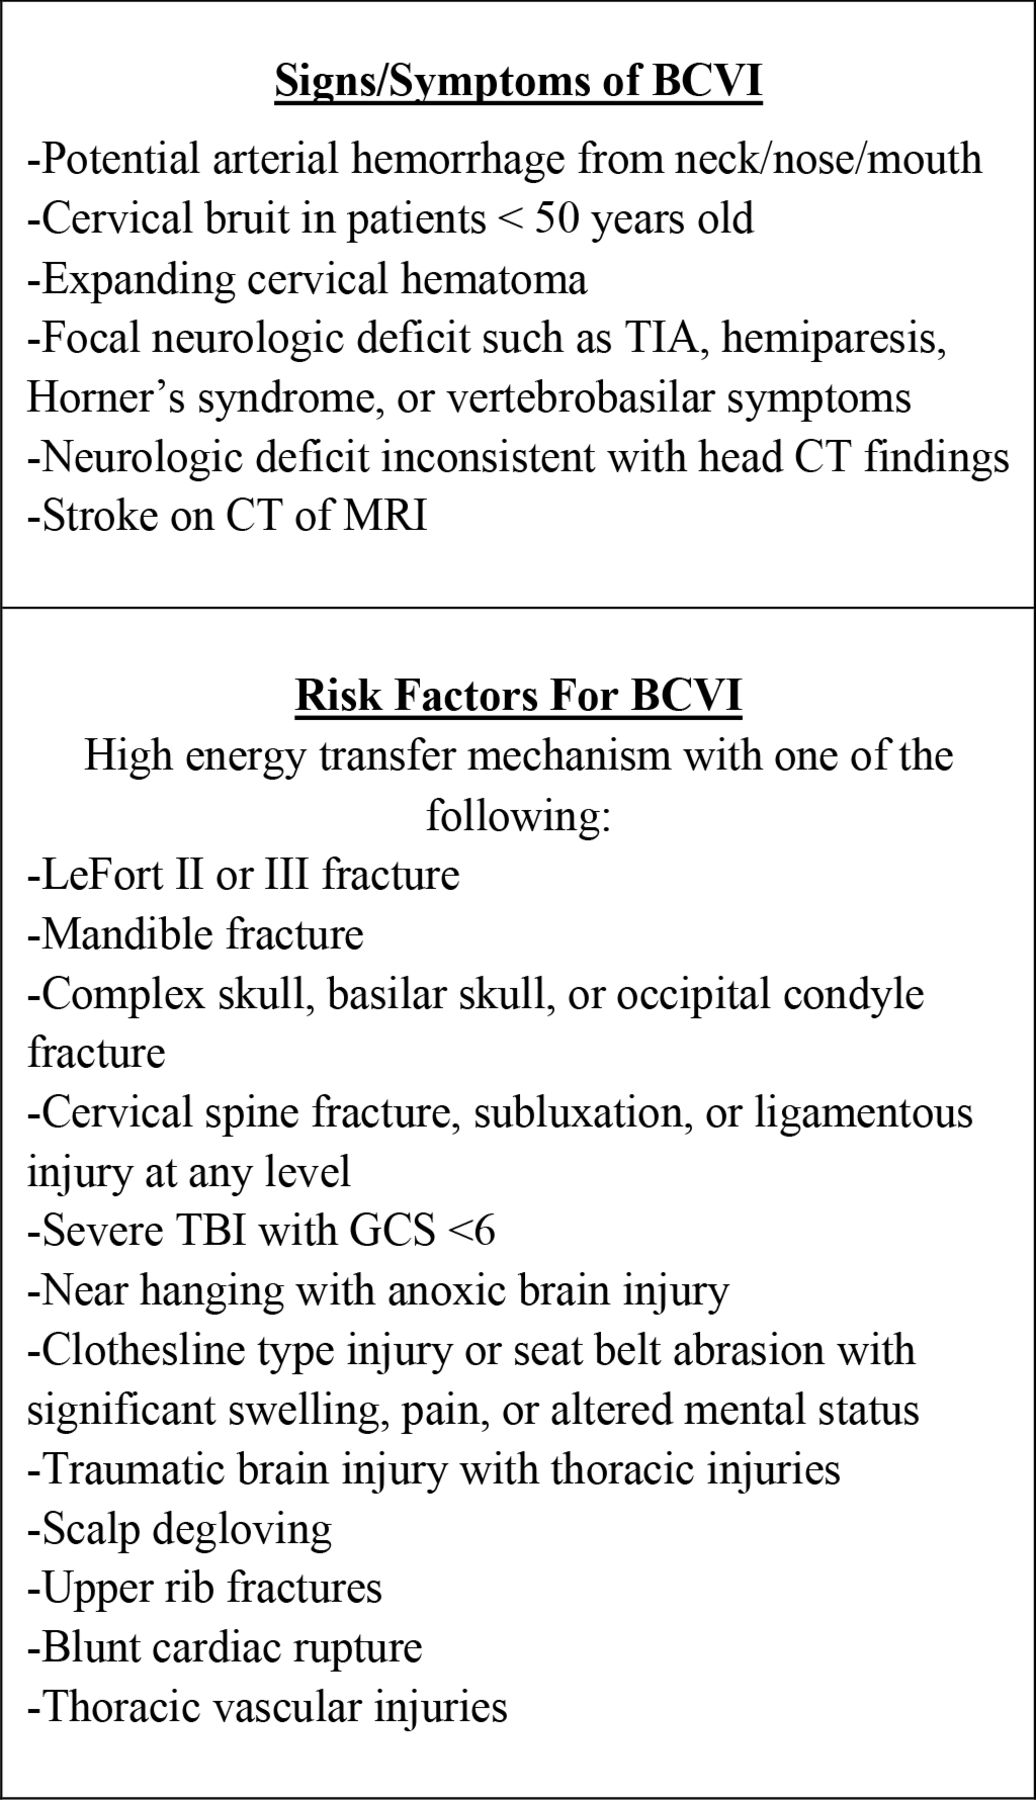
This institution implemented universal CTA of the neck to evaluate cerebral vascular injury in blunt trauma patients. In the 531 patients, 6% had cerebral vascular injury and 23% had incidental findings of which 22% required follow up. Another example of a test ordered has potential unanticipated downstream effect.
Show References
This commentary points out the missed opportunity to improve chronic hypertension care in the ED. A substantial number of patients seeking care for asymptomatic hypertension and an even larger cohort seen for other complaints who are also chronically untreated hypertensives leave the ED without a prescription for antihypertensives. ACEP and AHA say we should be treating these people and arranging follow up.
Show References
This case report describes a 2 week delayed hemorrhage from a lacerated profunda femoris artery after an intertrochanteric fracture that requires ORIF. The patient represented with anemia, pain and swelling in the surgically repaired hip. Pulses were still present. The authors conclude:
“The profunda femoris artery is the vessel most commonly involved in vascular complications associated with proximal femoral fractures because of its close anatomical relationship with the lesser trochanter. Delayed presentations may occur weeks after injury as repeated mechanical irritation from a displaced bone fragment leads to pseudoaneurysm formation and subsequent rupture.”
Show References
There is increasing evidence that burning lithium-ion batteries produce hydrofluoric acid (HF) and other fluoridated compounds. HF is a weak acid and thus it can penetrate deeper into tissue before causing complications. HF exposure causes irritation to the mucosa/skin and leads to pain out of proportion to the appearance of the burn/exposure. These exposures present a unique risk to first responders and care should be taken to wear appropriate PPE during these events. Regular medical gloves do not protect from exposure. Respiratory protection must be worn to prevent inhalation. Click for treatment options.
Show Additional Information
Show References
Reminder that the Bova Score (2 points each for heart rate over 110, SBP less than 90, RV strain on CT or echo, and elevated troponin) along with an elevated lactate and BNP can help predict outcomes in hemodynamically stable PE patients.
"Low risk (score <2):
Proceed with standard anticoagulation therapy. Standard outpatient or inpatient monitoring, as appropriate.
Intermediate risk (score 3–4): Consider closer monitoring (e.g., stepdown/ICU). Discuss the possibility of advanced therapies (e.g., thrombolysis) in select cases, especially if clinical status worsens.
High risk (score >4): Maintain continuous ICU monitoring with a clear plan for rapid intervention if clinical status worsens (e.g., hypotension, worsening hypoxia, arrhythmias). Strongly consider multidisciplinary team involvement and potential advanced therapies (e.g., systemic thrombolysis or catheter-directed therapies)."
Show References
A structured interview was conducted with families who had a loved one undergo a field terminated cardiac arrest in Denmark. What they found was pre-arrival instructions were very valued. And “After unsuccessful resuscitation, compassionate and unhurried communication was considered crucial.” I am sure this applies to prehospital and in hospital situations alike. Empathy and time are what these families need.
Show References
This secondary review of a prospective observational group of 1200 syncope/presyncope patients over age 40 found 5.6% experienced a significant adverse outcome within 30 days. These patients had no diagnosis after their ED evaluation. Their conclusion was admission to the hospital “increased the diagnostic yield for SAOs and accelerated time to diagnosis.”
Show References
This study conclusion states: “Prehospital epinephrine administration in patients with traumatic cardiac arrest was associated with increased survival to hospital discharge and prehospital ROSC.” When you investigate the methods, only 809 of the 22,105 patients in traumatic cardiac arrest actually received epinephrine. In the study country, EMS gets orders from base station physicians for epinephrine. Why did these 809 get the epinephrine and the other 97% did not? It is hard to know what to do with this data. It certainly doesn’t say epinephrine saves patients in traumatic cardiac arrest. More research is needed.
Show References
In a randomized pragmatic study of critically ill trauma patients, video laryngoscopy was successful in 88% of first pass attempts versus 68% in direct laryngoscopy.
Show References
This Japanese hospital has a CT scanner hybrid resuscitation room. They did a retrospective study comparing their blunt trauma patients to a Japanese trauma database. Their patients had a shorter time to operative or interventional procedure, slightly less PRBC use over 24 hours and similar 24 hour mortality.
Interesting concept. Not ready for adoption.
Show References
There is sound literature that older patients who board in the ED have higher rates of delirium, longer hospital stays, more complications and possibly higher mortality. Some institutions are starting to prioritize moving older patients upstairs ahead of others who may have been boarding longer in the ED. Hopefully some data will be out soon to see if this intuitive approach actually improves these outcomes.
Show References
This South African study looked at 219 trauma patients who required damage control surgery and, not surprisingly, low GCS, low pH and elevated lactate all were independently associated with mortality.
Show References
Question
The construction worker presents to the ED with this rash. What is it and what is the treatment?
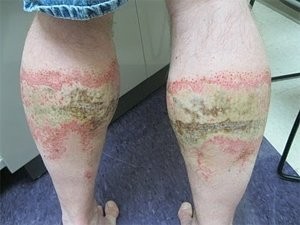
Show Answer
Show References
These authors used a database of 323 hospitals to find over 20,000 firearm injured patients. They looked at positive cultures to assess for post injury infection. Infection rate was 5%. Most infections were in the immediate post injury period. Those with surgical procedures on head, neck, lower abdomen, and spine were most likely to develop infection. Infection did not appear to be associated with increased mortality. Current guidelines recommend antibiotics for the first 24 hours post injury only.
Show References
Looking at a national EMS database, these authors found advanced airway management (intubation, cricothyrotomy, rescue devices) occurred in 4/1000 trauma patients. Firearm related injury and motorcycle crashes had the highest use rate. Firearm related injury had the highest use rate of cricothyrotomy. This data should help drive prehospital education.