
Search
Subscribe to daily UMEM Pearls (FREE!) via:
181-200 of 889 results with category "Critical Care"
Have you ever encountered an ESRD patient who missed dialysis because the patient "felt too sick to go to dialysis"? The patient then had hypotension from an infected catheter line? Do we give 30 ml/kg of balanced fluid now?
__________________________
Title: Outcomes of CMS-mandated ?uid administration among ?uid-overloaded patients with sepsis: A systematic review and meta-analysis.
Settings: This is a meta-analysis
Patients: Septic patients who have underlying fluid overload conditions (CHF or ESRD).
Intervention: intravenous fluid administration according to the mandate by the Center for Medicare/Medicaid as 30 ml per kilograms of bodyweight.
Comparison: fluid administration at less than 30 ml/kg of body weight.
Outcome: 30-day mortality, rates of vasopressor requirement, rates of invasive mechanical ventilation
Study Results:
- Random-effects meta-analysis of 5 studies, including 5804 patients. There were 5260 (91%) patients receiving non-aggressive IVF at < 30 ml/kg versus 544 (9%) patients received aggressive IVF at rates > 30 ml/kg.
- Patients who received aggressive IVF > 30 ml/kg were associated with 30-day all-cause mortality OR 1.42 (95% CI 0.88-2.3, P = 0.15, I2 =35%).
- The need for vasopressor during stay was similar: OR 0.69 (95%CI 0.42-1.15, P=0.21, I2 = 33%)
- The need for invasive mechanical ventilation during hospitalization was similar: OR 0.85 (95% CI 0.57-1.26, P = 0.42, I2 = 0)
- Both groups had similar ICU length of stay: Standard Difference in Means -0.002 (Very small magnitude), 95% CI -0.35 to 0.34, P= 0.99, I2 = 53)
- Similar hospital length of stay: Standard Difference in means -0.11 (small magnitude), 95% CI -0.62 to 0.38), P= 0.67, I2=77%
Discussion:
- All studies were retrospective studies, as it’s hard to do RCT when the treatment is required by guidelines. Although the studies were graded as high quality but there was still risk of bias.
- Until there is significant evidence to change the guidelines, please document thoroughly in your charts if you do not give sepsis patients who have fluid overload the required volume of IVF at 30 ml/kg.
- Consider early vasopressor.
Conclusion:
- Patients who have fluid overload and sepsis had similar outcomes when they were given IVF at rates < 30 ml/kg, compared to those given IVF > 30 ml/kg as required by CMS.
Show References
Point-of-care ultrasound compression of the carotid artery for pulse determination in cardiopulmonary resuscitation
Background:
Show References
Take Home:
This is essentially a secondary analysis of a previous prospective observational cohort study with high quality methods. The authors have an excellent discussion of the previous studies on this topic (which for those with an interest I highly recommend you read). They conclude that this study supports previous literature which I would think would be seemingly obvious, which is that those who are more ill to begin with have less tolerance of propofol (in a dose-independent relationship) in this and previous studies. Their use of IPTW extends the analysis on this large international population by addressing confounders in a novel way.
Their overall conclusion is that propofol is bad for the critically ill, and especially bad for those with pre-existing risk factors for intubation complications. I agree: This study suggests in even stronger terms that propofol should be used carefully and probably only in unhealthy patients when other options are unavailable.
Study Background and Characteristics
- INTUBE study1 was a prospective cohort study conducted from October 1, 2018, to July 31, 2019
- Enrolled consecutive “critically ill” patients over 8 week period at 197 clinical sites from all over the world. Critically ill was defined as those with “an underlying life-threatening condition causing cardio–respiratory failure or neurologic impairment”.
- Outcome of “cardiovascular instability/collapse” as one or more of the following events within 30 minutes of intubation start: (1199 of 2760 enrolled patients; 43.4%)
- systolic arterial pressure <65 mm Hg recorded at least once (collapse criteria) – 12.8%
- cardiac arrest (collapse criteria) – 7.8%
- systolic arterial pressure <90 mm Hg for >30 minutes – 24%
- new requirement or increase of vasopressors – 87.8%
- fluid bolus >15 ml/kg to maintain the target blood pressure – 13.2%
- STROBE Compliant
Findings
- CV-instability group were significantly older, high SOFA scores, and higher rates of ischemic heart disase, NYHA 3/4 heart failure, poor oxygenation (SPO2/FIO2 ration), pressors, fluid bolus/total, systolic/diastolic BP, and more commonly respiratory failure and cardiovascular instability as the reason for intubation.
- CV-stability group was less likely to receive propofol and at lower doses and more likely receive ketamine.
- Notably, CV-instability patients were less likely to be intubated by emergency physicians versus anesthesiology.
- Anesthesiologists were more likely to use propofol and more emergency medicine physicians using ketamine.
- Higher incidence of CV-instability in ischemic heart disease and heart failure, noninvasive ventilation and apneic oxygenation, and in the 30–45° head-up position.
- ICU mortality associated with:
- vasopressors/fluids without hypotension (OR, 1.47; 95% CI, 1.21–1.79)
- systolic blood pressure <90 mm Hg for >30 min despite vasopressors (OR, 2.65; 95% CI, 1.87–3.75)
- systolic blood pressure <65 mm Hg (OR, 1.89; 95% CI, 1.31–2.71)
- cardiac arrest (OR, 8.79; 95% CI, 5.46–14.7)
- Inverse Probability Treatment Weighting2 (IPTW) analysis found that the only treatment effect with significance associate with the entire CV-instability group was propofol usage (OR, 1.23; 95% CI, 1.02–1.49).
- No treatment effect, including propofol use or dosage, was associated with those meeting cardiovascular collapse criteria.
Show References
Traditionally, internal jugular and subclavian central line placement has required chest x-ray confirmation of correct placement (venous cavoatrial junction placement) as well as demonstrating lack of complication (no pneumothorax) prior to use of that central line. However, current evidence supports similar if not superior complication identification and placement confirmation with ultrasound,(1-7) allowing for a much quicker confirmation time than traditional chest x-ray, which can be vital in critically ill patients who need immediate medication administration.
Venous placement is confirmed with prompt visualization of microbubbles in the right atrium and ventricle with a rapid flush of 5-10 ml of agitated saline via the distal central line port. Additionally, if the opacification occurs <2 seconds after injection then the catheter tip is sufficiently distal in the central venous system to not require additional verification. Additional confirmation of lung sliding in both lung apices will rule out pneumothorax.
Some authors recommend checking the contralateral internal jugular vein to ensure that the central line catheter has not traveled up the internal jugular towards the head, however this may be redundant as long as the time from agitated saline injection to right atrial visualization of microbubbles is clearly less than 2 seconds.
Bottom Line: Utilization of ultrasound for central line placement confirmation is a relatively simple, rapid, safe, and accurate means of confirmation of venous catheter placement and catheter tip location, as well as ruling out pneumothorax complications.
Show Additional Information
Show References
Deep sedation in the ED has previously been associated with longer duration of mechanical ventilation, longer lengths of stay, and higher mortality.1 Current guidelines recommend light sedation, consistent with a goal RASS of -2 to 0, for most critically-ill patients in the ICU.2
The ED-SED3 multicenter, pragmatic, before-and-after feasibility study implemented an educational initiative (inservices, regular reminders, laminated sedation charts) to help target lighter sedation depths in newly-intubated adult patients without acute neurologic injury or need for prolonged neuromuscular blockade.
- 415 patients (196 pre-, 219 post-intervention), majority white (50%) and black (40%)
- Main reasons for intubation: sepsis, trauma, airway protection
- Majority of patients on fentanyl (85%) and propofol (76%), midazolam (20%)
After educational intervention:
- 21% fewer patients with deep sedation & 20% more patients achieving light sedation
- 10% decrease in comatose levels of sedation (RASS -4 to -5)
- Lower hospital mortality (20.4 vs 10%, p < 0.01)
- Similar rates of self-extubation and paralysis awareness
- More patients extubated in the ED, downgraded from ICU admission, and discharged from the ED
Even with the caveats of the confounding and bias that can exist in before-and-after studies, these results are consistent with prior sedation-related studies and offer more evidence to support for avoiding deep sedation in our ED patients. The study also demonstrates the importance of nurse-driven sedation in achieving sedation goals.
Bottom Line: Our initial care in the ED matters beyond initial stabilization and compliance with measures and bundles. Avoid oversedating intubated ED patients, aiming for a goal RASS of -2 to 0.
Show References
We previously posted on the COCA trial, which looked at empiric calcium administration in cardiac arrest. They studied 391 adult Danish cardiac arrest patients. The immediate and 30 day outcomes showed no benefit, and in fact strongly trended towards calcium being WORSE than placebo. This article provides the 6 month and 1 year follow up data. Surprise, surprise... calcium is still not looking good.
At 6 months survival non-significantly favored the placebo group, and at 1 year it significantly favored the placebo group. Neurologic outcome for those who survived was also no better, and perhaps slightly worse, in the calcium group.
Importantly, the trial excluded patients with "traumatic cardiac arrest, known or suspected pregnancy, prior enrollment in the trial, adrenaline prior to possible enrollment, and clinical indication for calcium at the time of randomization."
Bottom Line: The evidence continues to not support the routine empiric administration of calcium in cardiac arrest. Patients in whom there is an indication to give calcium (e.g. known ESRD, suspected hyperkalemia, etc) are excluded from these trials, and should likely still receive empiric calcium, but in undifferentiated cardiac arrest you can probably skip the calcium.
Show References
Diastolic Blood Pressure
- The diastolic blood pressure (DBP) is determined by vascular tone and remains relativley constant throughout the arterial system.
- A low DBP (< 50 mm Hg) suggests vasodilation and may be associated with an increased risk of myocardial ischemia and left ventricular dysfunction.
- In a recent trial, Ospina-Tascon and colleagues described the diastolic shock index (heart rate/DBP) and found that a DSI > 2.2 was associated with higher mortality in patients with septic shock.
- Take Home Point: pay attention to the DBP and, when low, consider initiation of vasopressors concomitant with fluid resuscitation.
Show References
Hemodynamic instability and cardiac arrest are major complications following endotracheal intubation. The mantra “resuscitate before you intubate” has prompted several studies of how to prevent this.
The PREPARE II trial is a multicenter ICU-based trial studying the effect of 500cc of crystalloid versus no crystalloid pre-emptively to prevent hypotension following endotracheal intubation. The study enrolled 1067 critically ill patients in United States ICUs. Some 60% of patient were intubated for respiratory failure and 20% were already on vasopressor. The primary induction drugs we etomidate and rocuronium. Importantly, urgent intubation was an exclusion. There were no differences in multiple endpoints including hypotension, new need for vasopressors, cardiac arrest, or 28-day mortality.
This was in some ways this in not unexpected and patients already in an ICU setting have typically received some form of fluid loading already. Being ICU based and primarily a more smoldering medical population this has limited application to more emergent and undifferentiated settings, but study underscores the need for a broad and nuanced view of what “resuscitate” means. Positive pressure may exacerbate hypovolemia, but the patient’s underlying disease, the effect of anesthetic drugs both by direct action via relief of pain, discomfort, or dyspnea may predominate if you think the patient is euvolemic.
Remember to dose anesthetics/sedatives/RSI drugs with an eye toward hemodynamics and consider starting vasopressors prior to intubation
Bottom Line:
-In a broad well-conducted ICU-based study a 500cc peri-intubation bolus doesn’t prevent hypotension
-Have a broad view of what resuscitation for intubation might entail
-Having fluid ready for intubation is helpful, hemodynamic dosing of drugs and having a plan for vasopressors might be even more helpful
-Applicability to ED environments is limited in this ICU-based trial
Show References
Have you ever wonder what patients feel after being intubated in the ED?
The study " Awareness With Paralysis Among Critically Ill Emergency Department Patients: A Prospective Cohort Study" aimed at answering just that.
Settings: Emergency Departments from 3 hospitals; This was a secondary analysis of a prospective trial.
Patients:
Patients who received neuromuscular blockade in ED
Intervention: None.
Comparison: None.
Outcome: Primary outcome was Awareness while paralyzed, secondary outcome was Perceived threat, which is considered the pathway for PTSD.
Study Results:
The study evaluated 388 patients. There were 230 (59%) patients who received rocuronium.
Patients who received rocuronium (5.5%, 12/230) were more likely to experience awareness than patients receiving other neuromuscular blockade (0.6%, 1/158).
Patients who experienced awareness during paralysis had a higher threat perception score that those who did not have awareness (15.6 [5.8] vs. 7.7 [6.0], P<0.01).
A multivariable logistic regression, after adjustment for small sample size, showed that Rocuronium in the ED was significantly associated with awareness (OR 7.2 [1.39-37.58], P = 0.02).
Discussion:
With the increasing use of rocuronium for rapid sequence intubation in the ED, clinicians should start to pay more attention to the prevalence of awareness during paralysis. According to the study, patients reported pain from procedures, being restrained, and worst of all feelings of impending death.
One of the risk factors for awareness during paralysis would be the long half-life of rocuronium, compared to that of succinylcholine. Therefore, clinicians should consider prompt and appropriate dosage of sedatives for post-intubation sedation. Previous studies showed that a mean time from intubation till sedatives was 27 minutes (2), and propofol was started at a low dose of 30 mcg/kg/min for ED intubation (3).
Conclusion:
Approximately 5.5% of all patients or 4% of survivors of patients who had invasive mechanical ventilation in the ED experienced awareness during paralysis. They also were at high risk for PTSD.
Show References
Tachyarrhythmias in the setting of high-dose vasopressors due to septic shock are not uncommon. Aside from amiodarone, some providers may not know of alternative therapeutic options in the setting of septic shock. In addition, some may view the use of a beta-blocker as counter-intuitive or counter-productive in the setting of norepinephrine usage.
However, there have been multiple smaller studies evaluating using esmolol (and other short-acting beta-blockers) in the setting of tachycardia, septic shock and pressors. Outcomes regarding the theoretical benefits of beta-blockade in sepsis (i.e. decreased mortality/morbidity 2/2 decreased sympathetic innervation, inflammation, myocardial demand etc.) have been varied. However, esmolol has been demonstrated multiple times to be effective at reducing heart rate without significant adverse outcomes (i.e. no sig diff in mortality, refractory shock, or time on vasopressors).
Caveats/pitfalls
-most of the studies discuss “adequate resuscitation” prior to initiation of esmolol
-not studied in patients that also had significant cardiac dysfunction
-be aware that esmolol gtts can be a lot of volume and pts can become volume overloaded if boarding in the ED for an extended period of time
Show References
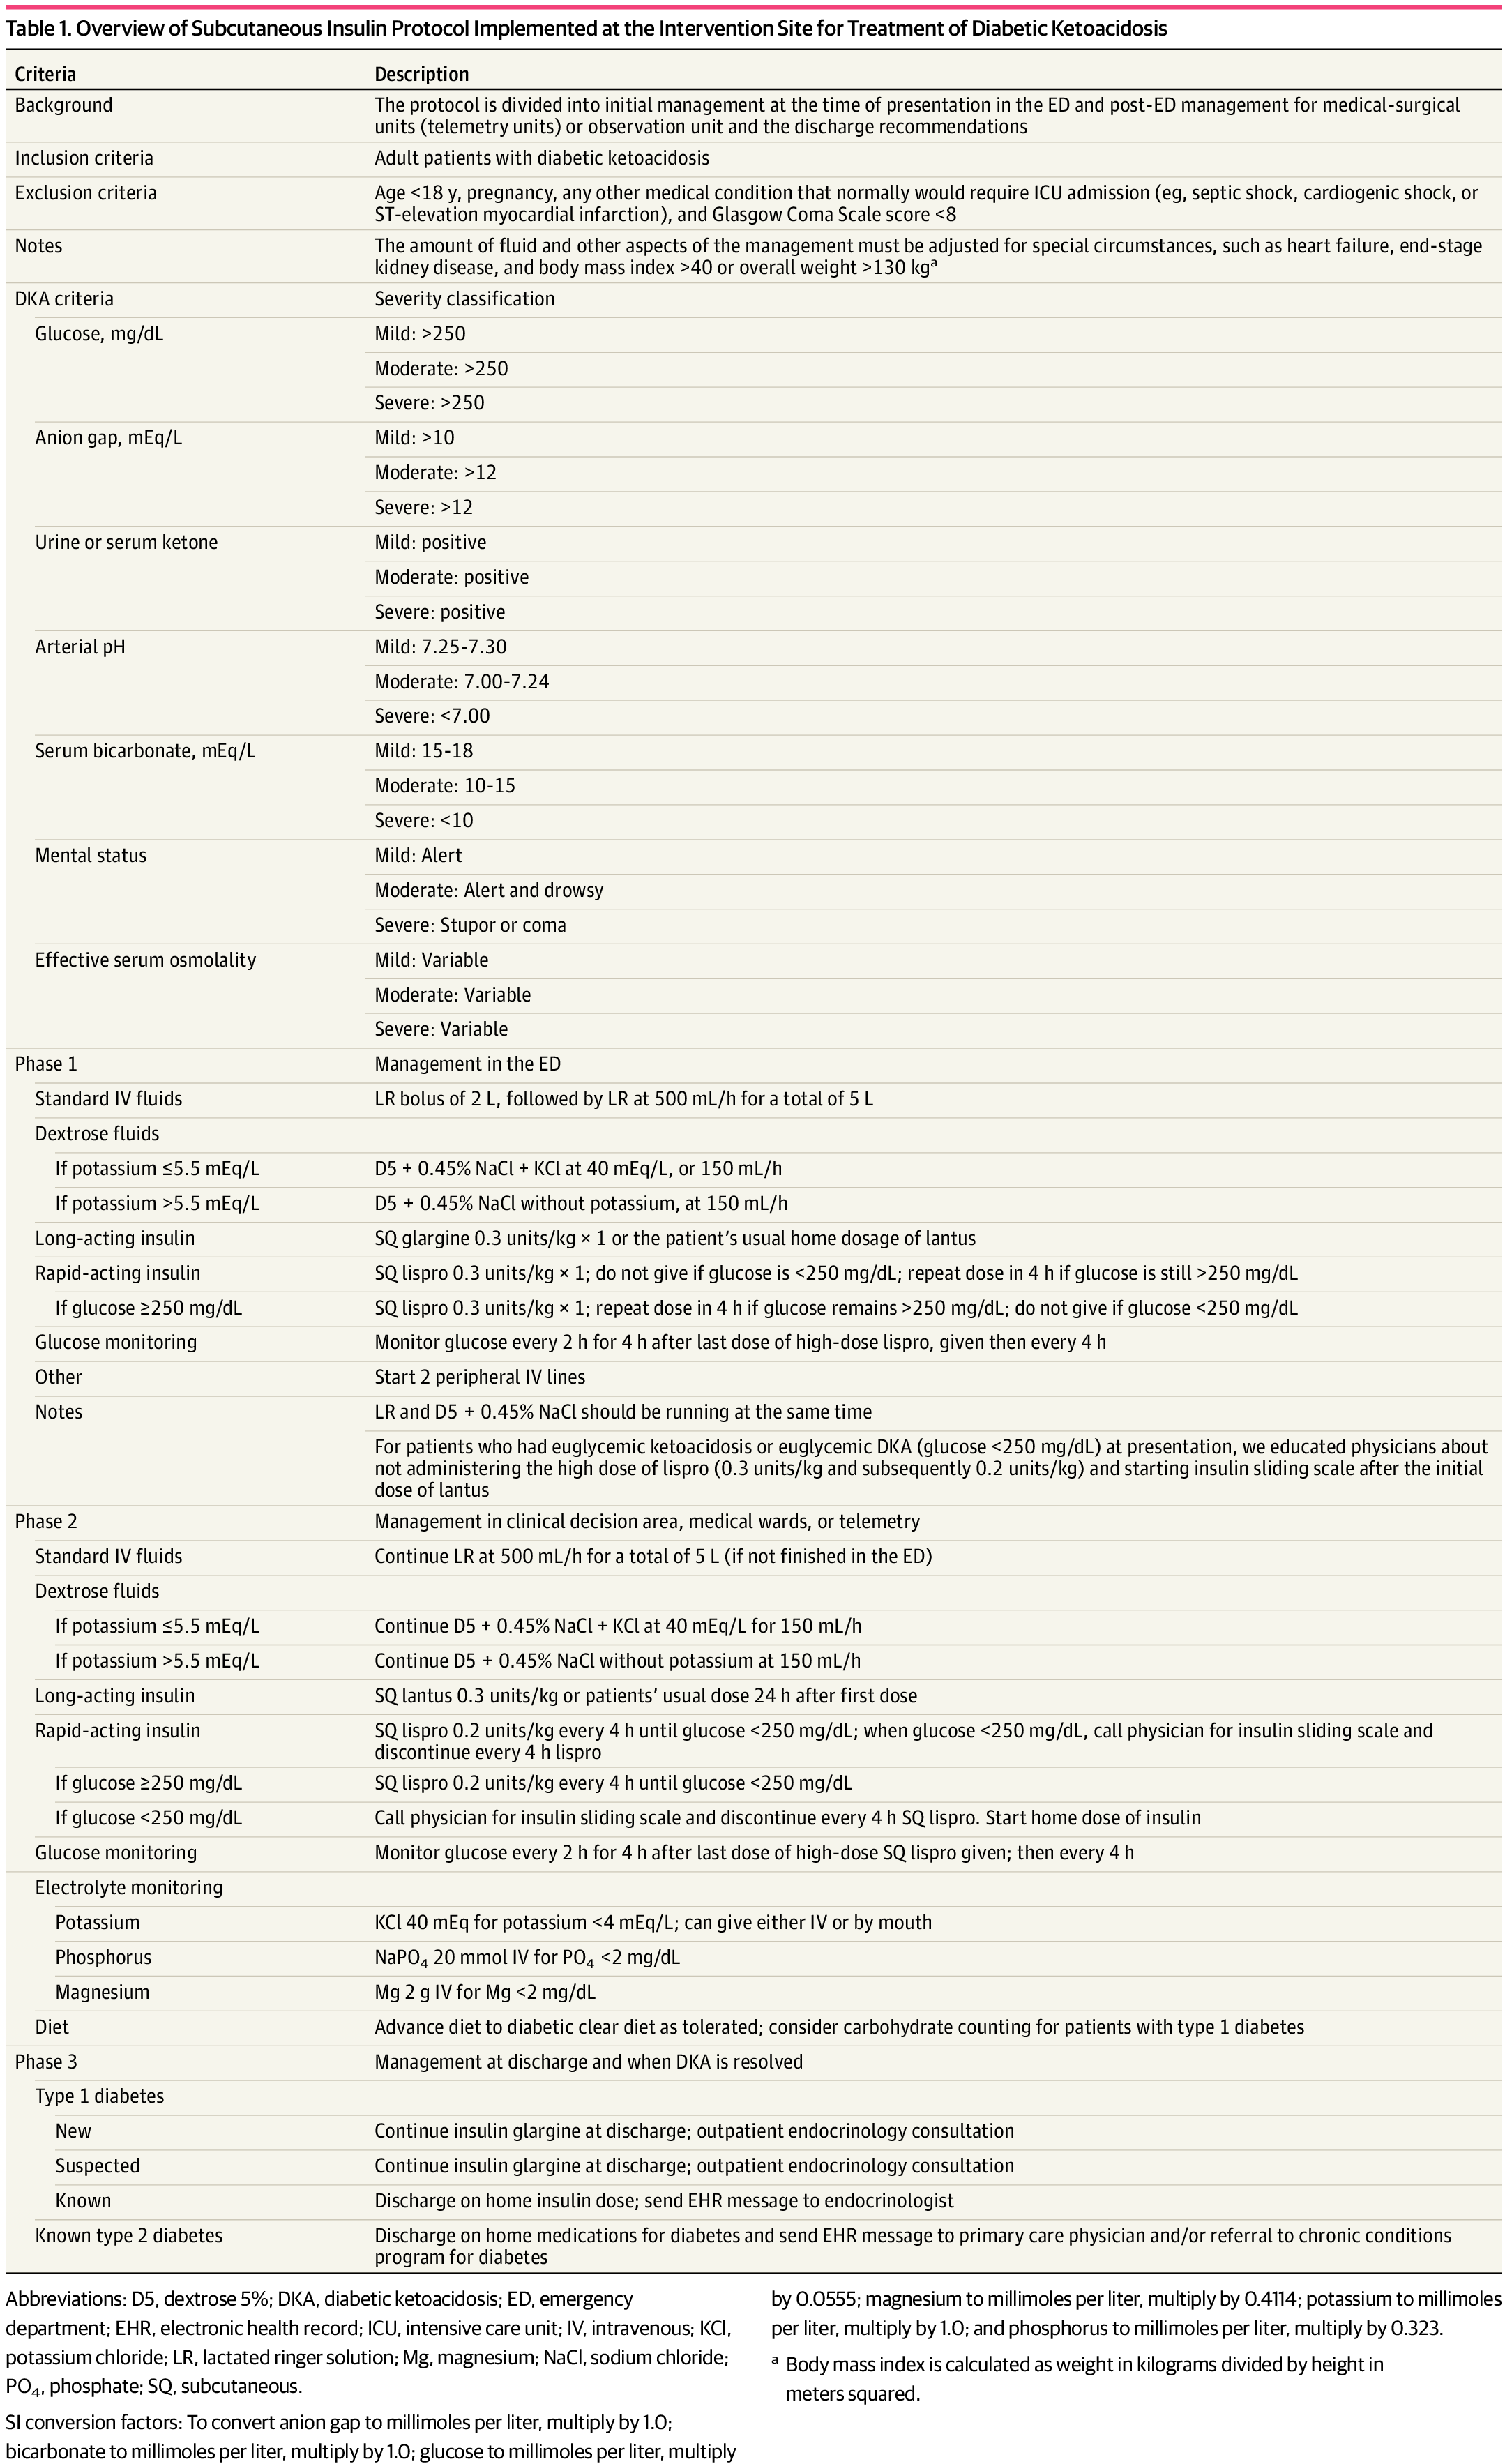
Background: It is classically taught that the tenets of DKA management are IV fluids, electrolyte repletion, and an insulin infusion that is titrated until approximately 2 hours after anion gap closure, when long-acting subcutaneous insulin is administered if the patient is tolerating oral intake. It has been previously found that earlier administration of subcutaneous long-acting insulin can shorten the time to anion gap closure, while other small studies have noted similar efficacy in subcutaneous insulin compared to IV in mild/moderate DKA.
A recent JAMA article presents a retrospective evaluation of a prospectively-implemented DKA protocol (see "Full In-Depth" section) utilizing weight-based subcutaneous glargine and lispro, rather than IV regular insulin, as part of initial and ongoing floor-level inpatient treatment.
When compared to the period before the DKA protocol:
- ICU admissions decreased (27.9% from 67.8%, p<0.001)
- There was no difference in overall amount of insulin and time to anion gap closure
- There was no difference in 30-day mortality
- There was no difference in incidence of hypoglycemc events.
The only exclusion criteria were age <18 years, pregnancy, and presence of other condition that required ICU admission.
Bottom Line: Not all DKA requires IV insulin infusion.
At the very least, we should probably be utilizing early appropriate-dose subcutaneous long-acting insulin. With ongoing ICU bed shortages and the importance of decreasing unnecessary resource use and hospital costs, perhaps we should also be incorporating subcutaneous insulin protocols in our hospitals as well.
Show Additional Information
Show References
Although it is well-documented that there is no true "maximum" dose of vasopressor medications, further blood pressure support as doses escalate to very high levels tends to be limited. As such, debate has raged in Critical Care as to when is the "right" time to start a second vasoactive medication. The VASST trial (Russell et al, NEJM, 2008) is considered to be the landmark trial in this area, and found a trend towards improvement with early addition of vasopressin to norepinephrine, but no statistically significant difference, and may have been underpowered.
Partly as a result of VASST, the pendulum has tended to swing towards maximizing a single vasoactive before adding a second over the past decade. The relatively high cost of vasopressin in the US has also driven this for many institutions. However, more recently a "multi-modal" approach, emphasizing an earlier move to second, or even third, vasoactive medication, is increasingly popular. Although cost is often prohibitive for angiotensin-2 given controversial benefits, many now advocate for targeting adrenergic receptors (e.g. with norepinephrine or epinephrine), vasopressin receptors (e.g. with vasopressin or terlipressin) and the RAAS system (e.g. with angiotensin 2) simultaneously in patients with refractory shock. A recent review by Wieruszewski and Khanna in Critical Care (see references) outlines this approach well.
Bottom Line: When to add a second vasoactive medication (e.g. vasopressin) for patients with refractory shock after a first vasoactive is controversial and not known. Current practice is trending towards earlier addition of a second (or third) agent, especially if targeting different receptors, but there is limited high-quality evidence to support this approach. Many practicioners (including this author) still follow VASST and consider vasopressin once doses of around 5-15 micrograms/min (non-weight based) of norepinephrine are reached.
Show References
Vasopressor Tips in the Critically Ill
- Critically ill patients often require the administration of vasopressors to maintain adequate organ perfusion.
- A few tips to consider when administering vasopressors include:
- Titrate to mean arterial blood pressure (MAP) or diastolic blood pressure goals. Systolic blood pressure (SBP) is not a key driver of perfusion pressure.
- As vasopressors also result in venoconstriction and can increase venous return, early initation may limit the need for overly aggressive fluid resuscitation.
- Vasopressors can be safely administered through an appropriately placed peripheral venous catheter.
- There is no maximal dose of vasopressors.
- Consider vasopressors with a different mechanism of action in patients with persistent shock refractory to the initial vasopressor agent.
Show References
Background:
Lung-protective ventilation with low-tidal volume improves outcome among patients with Acute Respiratory Distress Syndrome. The use of low tidal volume ventilation in the Emergency Departments has been shown to provide early benefits for critically ill patients.
Methodology:
A systemic review and meta-analysis of studies comparing outcomes of patients receiving low tidal volume ventilation vs. those who did not receive low tidal volume ventilation.
The authors identified 11 studies with approximately 11000 patients. The studies were mostly observational studies and there was no randomized trials.
The authors included 10 studies in the analysis, after excluding a single study that suggested Non-low tidal volume ventilation was associated with higher mortality than low tidal volume ventilation (1).
Results:
Comparing to those with NON-Low tidal volume ventilation in ED, patients with Low-Tidal volume ventilation in ED were associated with:
- Significant lower risk of death (OR 0.80, 95% CI 0.72-0.88, I2 = 0%),
- Lower risk of ARDS (OR 0.57, 95% CI 0.44-0.75, I2 = 21%),
- Shorter ICU length of stay (Mean Difference -1.19 days [-2.38, -0.11]),
- Shorter ventilator-free days (-1.03 days, [-1,74, -0.32]).
Discussion:
- If the outlying study by Prekker et al was included, there as no significant difference in mortality.
- Tidal volume in ED has been steadily decreased. It was approximately 9 ml/kg of predicted body weight when reported in 2009, and was approximately 6.5 mg/kg PBW in 2018.
- Most ventilator settings in the ED would be continued in the ICU.
Conclusion:
Although there was low quality of evidence for low tidal volume ventilation in the ED, Emergency clinicians should continue to consider this strategy.
Show References
-If the patient is able to maintain mentation/airway/SpO2/hemodynamics and cough up blood, intubation is not immediately necessary
- an ETT will actually reduce the diameter of the airway and can impede clearance and precipitate respiratory failure
-If you do intubate, intubate with the largest ETT possibly to faciliate bronchoscopic interventions and clearance of blood
- Men: 8.5 or above; Women: 8.0 or above
-The CT scan that typically needs to be ordered is a CTA (not CTPA) with IV con
- 90% of life-threatening hemoptysis from the bronchial arteries
-See if you can find prior/recent imaging in the immediate setting (e.g. pre-existing mass/cavitation on R/L/upper/lower lobes)
- having a level of suspicion for location/lateralization is helpful for the performing bronchoscopist to allow them to empirically occlude a location with an endobronchial blocker in a crashing hypoxemic patient if visualization is difficult 2/2 blood
-Get these meds ready before the bronchoscopist gets to the bedside to expedite care:
- iced/cold saline, thrombin, code-dose epi (which will be diluted)
- there is also some (not great) data for intravenous TXA and improved outcomes
-If the pt's vent suddenly has new high peak pressures or decreased volumes after placement of endobronchial blocker, be concerned that the blocker has migrated
- this can happen even with 1 cm movement of the ETT or blocker, or extension of the patient's neck
- know where the ETT is secured as well as the endobronchial blocker (analagous to locking of a transvenous pacer)
- pts with endobronchial blockers should also be on continuous neuromuscular blockade
Show References
Encountered a situation in CCRU where we needed to prepare for a patient exsanguinating from gastric varices, and found a great summary of the different types of gastroesophageal balloons from EMRAP.
Summary: https://www.youtube.com/watch?v=Yv4muh0hX7Y
More in depth video on the Minnesota tube: https://www.youtube.com/watch?v=4FHIiA_doWU
Nice review article: https://www.sciencedirect.com/science/article/abs/pii/S0736467921009136
Based on prior studies1 indicating possibly improved outcomes with vasopressin and steroids in IHCA (Vasopressin, Steroids, and Epi, Oh my! A new cocktail for cardiac arrest?), the VAM-IHCA trial2 compared the addition of both methylprednisolone and vasopressin to normal saline placebo, given with standard epinephrine resuscitation during in hospital cardiac arrest (IHCA).
The use of methylprednisolone plus vasopressin was associated with increased likelihood of ROSC: 42% intervention vs. 33% placebo, RR 1.3 (95% CI 1.03-1.63), risk difference 9.6% (95% CI 1.1-18.0%); p=0.03.
BUT there was no increased likelihood of favorable neurologic outcome (7.6% in both groups).
Recent publication on evaluation of long-term outcomes of the VAM-ICHA trial3 showed that, at 6-month and 1-year follow-up, there was no difference between groups in:
- Survival
- Favorable neurologic outcome (CPC 1 or 2; mRS 0-3)
- Health-related quality of life (per EQ-5D5L survey)
Bottom Line: Existing evidence does not currently support the use of methylprednisolone and vasopressin as routine code drugs for IHCA resuscitation.
Show Additional Information
Show References
ED Low-Tidal Volume Ventilation
- Low-tidal volume ventilation (LTVV) reduces mortality in patients with ARDS and may reduce mortality in patients without ARDS.
- Recent literature has highlighted the importance of initial ED ventilator settings, as these often persist for many hours after ICU admission.
- But..does the use of LTVV in the ED really make a difference?
- A recent systematic review and meta-analysis sought to evaluate the use of LTVV in the ED and the impact upon clinical outcomes.
- In short, the use of LTVV in the ED was associated with an increase in the use of LTVV in the ICU, decreased occurrence of ARDS after admission, shorter ICU and hospital lengths of stay, decreased duration of mechanical ventilation, and decreased mortality.
- Take Home Point: The use of LTVV in the ED makes a difference!
Show References
During the height of the pandemic, a large proportion of patients who were referred to our center for VV-ECMO evaluation were on Airway Pressure Release Ventilation (APRV). Does this ventilation mode offer any advantage? This new randomized control trial attempted to offer an answer.
---------------
1.Settings: RCT, single center
2. Patients: 90 adults patients with respiratory failure due to COVID-19
3. Intervention: APRV with maximum allowed high pressure of 30 cm H20, at time of 4 seconds. Low pressure was always 0 cm H20, and expiratory time (T-low) at 0.4-0.6 seconds. This T-low time can be adjusted upon analysis of flow-time curve at expiration.
4. Comparison: Low tidal volume (LTV) strategy according to ARDSNet protocol.
5. Outcome: Primary outcome was Ventilator Free Days at 28 days.
6.Study Results:
- Baseline characteristics were similar. At randomization, PF ratio for APRV group = 140 (SD 42) vs. 149 (SD 50) for LTV group.
- Median Ventilator Free Day for APRV group: 3.7 [0-15] days vs. 5.2 [0-19] for LTV group ( P = 0.28)
- APRV group had higher PaO2/FiO2 ratio during first 7 days (mean difference = 26, P<0.001)
- ICU length of stay for APRV group: 9 [7-16] vs. 12 [8-17] days (P = 0.17)
- Severe hypercapnia (Pco2 at ≥ 55 along with a pH < 7.15): APRV group = 19 (42%) vs. LTV = 7 (15%), P = 0.009.
- Death at 28 days: 35 (78%) for APRV group, vs. 27 (60%) for LTV group ( P = 0.07)
7.Discussion:
- Hypercapnea was transient and was mostly due to implementation of the ventilator settings. The protocol recommended reduction of T-high to allow more ventilation, but most clinicians did not want to shorten the T-High, but instead opted for higher T-low.
- Although the number of barotrauma were similar in both group, all 4 cases of barotrauma in the APRV group occurred within a very short period of time (3 weeks), prompted the safety monitoring board to recommend stopping recruitment for COVID-19 patients.
8.Conclusion:
APRV was not associated with more ventilator free days or other outcomes among patients with COVID-19, when compared to Low Tidal Volume strategies in this small RCT.
Show References
The use of catecholamines following OHCA has been a mainstay option for management for decades. Epinephrine is the most commonly used drug for cardiovascular support, but norepinephrine and dobutamine are also used. There is relatively poor data in their use in the out of hospital cardiac arrest (OHCA). This observational multicenter trial in France enrolled 766 patients with persistent requirement for catecholamine infusion post ROSC for 6 hours despite adequate fluid resuscitation. 285 (37%) received epinephrine and 481 (63%) norepinephrine.
Findings
- Deaths from refractory shock (35% vs. 9%, P<0.001) and Recurrent cardiac arrest (9% vs. 3%, P<0.001) were higher in the epinephrine group
- In both univariate/multivariate analyses, use of epinephrine was significantly associated with:
- All-cause mortality during the hospital stay (83% vs. 61%, P<0.001) / (OR 2.6, 95%CI 1.4–4.7, P=0.002)
- Cardiovascular-specific mortality (44% vs. 11%, P<0.001) / (aOR 5.5, 95%CI 3.0–10.3, P<0.001)
- Frequency of unfavorable neurological outcomes (37% vs. 15%, P<0.001) / (aOR 3.0, 95%CI 1.6–5.7, P=0.001)
- While propensity scoring and match analysis largely confirmed these findings, further regression did not associate epinephrine with all-cause mortality.
Limitations:
- Epinephrine arm: significantly longer time to ROSC, lower blood pH at admission, higher rates of unshockable rhythm, higher levels of arterial lactate at admission, lower LV ejection fraction, and higher levels of myocardial dysfunction.
- Propensity matching always has the potential for confounders.
Summary:
Norepinephrine may be a better choice for persistent post-arrest shock. However, this study is not designed to sufficiently address confounders to recommend abandoning epinephrine altogether, but it does give one pause.