
Search
Subscribe to daily UMEM Pearls (FREE!) via:
A recent RCT published in JAMA evaluated the use of sodium bicarbonate for in-hospital cardiac arrest and found no differences in rates of ROSC, 30-d survival, or survival with a favorable neurologic outcome. The sodium bicarbonate group had higher rates of adverse events such as alkalosis and hypernatremia.
Bottom line: Routine use of sodium bicarbonate during cardiac arrest is not recommended.
Additional Information
Study Design: This was a randomized, parallel-group, double-blind, placebo-controlled trial in Denmark from 2023-2026 that included adult patients who received >/= 1 dose of epinephrine during in-hospital cardiac arrest. Patients with a DNR order, prior enrollment, invasive mechanical circulatory support, or a clinical indication for sodium bicarbonate (SB) were excluded. Patients were randomized 1:1 to either 50 mL (50 mmol) of sodium bicarbonate 8.4% or 50 mL of sodium chloride 0.9% for up to a max of 2 doses.
Population: A total of 779 patients were eligible for the primary analysis. The median age of the population was 74, most were males (65%), and majority were witnessed arrests (76%). Median time to epinephrine was 6 minutes, and median time to the trial drug was 8 minutes. Most arrests (66%) occurred on the hospital ward and 14% had acidosis prior to cardiac arrest.
Results: There was no difference in the rate of ROSC between groups, 30-day survival, or survival with a favorable neurologic outcome (Table 1). The sodium bicarbonate group had higher rates of alkalosis (35% vs 20%) and hypernatremia (42% vs. 29%).
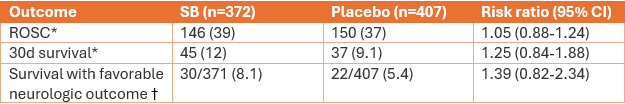
*Reported as n(%) †Reported as No./total No.(%)
References
Granfeldt A, Kirgegaard BL, Vallentin MF et al. Sodium bicarbonate for in-hospital cardiac arrest: a randomized clinical trial. JAMA. 2026;336(8):647-654. doi:10.1001/jama.2026.10628